
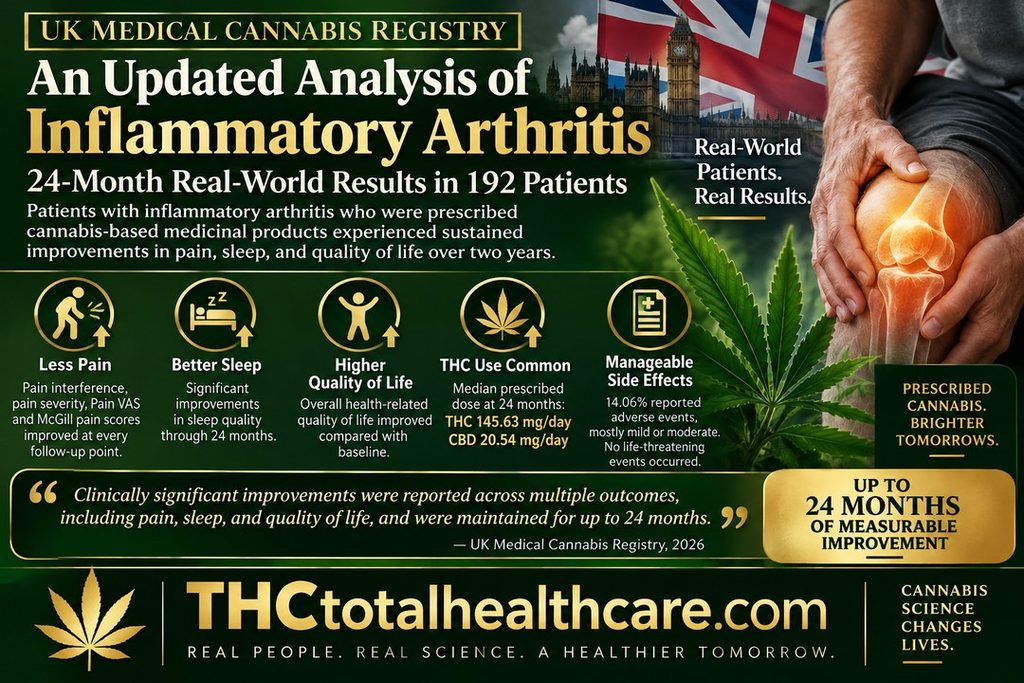
UK Medical Cannabis Registry: An Updated Analysis of Inflammatory Arthritis

A new analysis from the UK Medical Cannabis Registry reports sustained improvements in pain, sleep, and health-related quality of life among patients with inflammatory arthritis who were prescribed cannabis-based medicinal products.

The study followed 192 patients for up to 24 months. Improvements were reported across multiple pain measures at every follow-up point, including pain severity, pain interference, and overall pain scores. Sleep quality and general quality of life also improved compared with baseline.

Notably, many patients were prescribed THC-containing products, including dried cannabis flower and oils. The findings add long-term real-world evidence that prescribed cannabis medicines may help some people living with inflammatory arthritis.

“Aim: Cannabis-based medicinal products (CBMPs) are an emerging therapeutic option for pain in inflammatory arthritis, yet clinical evidence remains limited. This study aimed to evaluate changes in pain-specific and general health-related outcomes in patients with inflammatory arthritis treated with CBMPs and to characterize the safety profile by examining the incidence and nature of adverse events.

Methods: Patients treated with CBMPs for inflammatory arthritis-associated pain for ⩾24 months were identified from the UK Medical Cannabis Registry. Primary outcomes included changes in patient-reported measures: Brief Pain Inventory (BPI), Pain Visual Analogue Scale (Pain VAS), Short-Form McGill Pain Questionnaire 2 (SF-MPQ-2), EuroQol 5-dimension 5-level (EQ-5D-5L), Generalized Anxiety Disorder-7 (GAD-7), and Single-Item Sleep Quality Scale (SQS) at 1, 3, 6, 12, 18, and 24 months vs baseline. Adverse events were recorded and analysed. Statistical significance was set at P < .050.

Results: A total of 192 patients met inclusion criteria. The CBMP initiation was associated with improvements in BPI Interference, BPI Severity, Pain VAS, SF-MPQ-2, SQS, and EQ-5D-5L index values at all follow-up time points (P < .010) and in GAD-7 scores up to 3 months (P < .001). Twenty-seven patients (14.06%) reported 296 adverse events: 126 (42.57%) mild, 132 (44.59%) moderate, and 38 (12.84%) severe. No life-threatening events occurred.

Conclusion: The CBMP therapy was associated with reductions in pain and improvements in health-related quality of life among individuals with inflammatory arthritis. Although causality cannot be inferred from this observational design, these findings support the need for randomized controlled trials to determine the efficacy of CBMPs for inflammatory arthritis-related pain.”

https://pubmed.ncbi.nlm.nih.gov/42724108

“Overall, results of this study demonstrate reductions in pain severity and improvements in HRQoL for patients receiving CBMP treatment for chronic pain linked to inflammatory arthritis over a period of 24 months of follow-up. The CBMPs were generally well-tolerated, although the risk of AE and individual responses should be considered before commencing CBMP treatment.”

https://journals.sagepub.com/doi/10.1177/11795441261480709

The Endocannabinoid System is No Longer the Limiting Factor: Why Policy and Stigma Continue to Delay Cannabinoid-Based Medicine

The science of the endocannabinoid system has advanced dramatically, but cannabinoid-based medicine is still being held back by forces outside the laboratory. This new Clinical Therapeutics commentary argues that the biological understanding of the endocannabinoid system is no longer the main limiting factor. The larger barriers are now policy, regulation, funding, access, and stigma.

According to the authors, restrictive and fragmented rules make cannabinoid research harder to conduct, while limited access to standardized products complicates rigorous clinical trials. At the same time, stigma within medicine can discourage research, education, prescribing, and open discussion with patients.

The message is simple: the remaining evidence gaps are not purely scientific. They are also structural. If cannabinoid-based medicine is going to move forward, policy and medical culture will have to catch up with what researchers already understand about the endocannabinoid system.

“Purpose: To examine whether the persistent gap between the extensive mechanistic knowledge of the Endocannabinoid System (ECS) and the limited number of high-quality randomized clinical trials of cannabinoid-based therapies primarily reflects scientific uncertainty or, instead, structural regulatory, economic, and social barriers.

Methods: This commentary critically synthesizes historical, regulatory, and contemporary evidence on cannabinoid research, integrating data from regulatory documents, international policy reports, clinical and observational studies, systematic reviews, and qualitative investigations. Particular emphasis is placed on barriers affecting access to standardized products, conduct of randomized clinical trials, public funding, product standardization, and healthcare professionals’ perceptions.

Findings: Although the ECS has been extensively characterized for more than three decades and cannabinoids demonstrate plausible pharmacological mechanisms across multiple therapeutic areas, clinical translation remains disproportionately limited. Persistent regulatory restrictions, inherited from prohibition policies, continue to delay access to standardized research material, increase the cost and complexity of clinical trials, and shift evidence generation toward observational designs. Regulatory fragmentation further compromises product standardization and study reproducibility, whereas persistent social and professional stigma reduces research activity, medical education, prescribing confidence, and patient disclosure, perpetuating a self-reinforcing cycle between limited evidence generation and clinical distrust.

Implications: The principal obstacle to cannabinoid-based medicine is no longer the biological understanding of the ECS but the structural environment surrounding cannabinoid research. Progress toward evidence-based clinical implementation will depend on regulatory harmonization, greater public investment in randomized clinical research, standardized pharmaceutical-quality products, and educational initiatives capable of reducing stigma among healthcare professionals. Recognizing the structural rather than scientific origin of the evidence gap is essential for informing future research priorities, editorial policies, and international regulatory strategies.”

https://pubmed.ncbi.nlm.nih.gov/42728140

“The ECS is no longer the main obstacle to cannabinoid therapeutics. Stigma and regulation continue to delay clinical translation. Standardized clinical research requires international regulatory reform. Medical education is crucial for evidence-based cannabinoid therapies.”

https://www.clinicaltherapeutics.com/article/S0149-2918(26)00317-6/fulltext