Standardized Curcuma longa-Cannabis sativa extract derived from a traditional Thai formulation for psoriasis: anti-inflammatory activity, keratinocyte modulation, and skin-targeted delivery

A new study tested a standardized combination of Curcuma longa (turmeric) and Cannabis sativa derived from a traditional Thai topical formulation for psoriasis. The combined extract contained curcuminoids, ar-turmerone and cannabidiol, including 35.47 mg/g CBD, and was evaluated for anti-inflammatory activity, effects on psoriasis-related keratinocytes and its ability to remain concentrated in the skin.

At 12.5 µg/mL, the combined extract reduced nitric oxide production by 48.97% and PGE₂ production by 91.15%. It also altered psoriasis-associated gene expression in TNF-α/IL-17A-stimulated keratinocytes, showing activity against several biological processes involved in psoriasis.

The skin-delivery experiments found strong deposition of the extract’s markers in the skin, with none detected in the receptor compartment during the 24-hour test. The authors concluded that the standardized turmeric–cannabis combination showed anti-inflammatory, psoriasis-relevant and skin-targeted activity supporting further development as a localized phytotherapeutic approach for psoriasis.

“Ethnopharmacological relevance: Curcuma longa rhizomes and Cannabis sativa leaves are traditionally combined in Thai topical remedies using cottonseed oil. However, the pharmacological basis and dermal delivery of this combination remain unclear.

Aim of the study: This study evaluated a standardized Thai CL-CS combined extract (CLCS) by integrating phytochemical characterization, psoriasis-relevant biological activities, and ex vivo skin deposition and permeation, with comparison to the single extracts.

Materials and methods: CLCS was standardized by validated HPLC using curcuminoids, ar-turmerone, and cannabidiol as markers. Anti-inflammatory activity was evaluated in RAW264.7 macrophages, while psoriasis-relevant activity was assessed in TNF-α/IL-17A-stimulated HaCaT keratinocytes. Skin deposition and permeation were evaluated using porcine ear skin and Franz diffusion cells.

Results: CLCS contained bisdemethoxycurcumin (18.79 ± 1.54 mg/g), demethoxycurcumin (12.89 ± 1.02 mg/g), curcumin (22.12 ± 1.62 mg/g), ar-turmerone (75.35 ± 3.94 mg/g), and cannabidiol (35.47 ± 2.39 mg/g). IC50 values were 41.22 ± 1.70 and 22.91 ± 0.51 μg/mL in HaCaT and RAW264.7 cells, respectively. At 12.5 μg/mL, CLCS inhibited NO and PGE2 production by 48.97 ± 0.88% and 91.15 ± 3.66%, respectively, and modulated psoriasis-associated genes. Cottonseed oil containing 20% DG achieved the highest skin deposition of BCM, DCM, and CM, with no detectable markers in the receptor compartment over 24 h.

Conclusions: Standardized CLCS exhibited anti-inflammatory and psoriasis-relevant activities and preferential skin deposition, supporting its potential as a localized phytotherapeutic approach for psoriasis.”

https://pubmed.ncbi.nlm.nih.gov/42772617

“The present study provides an integrated chemical, biological, and skin-targeted delivery evaluation of a standardized CLCS co-extract derived from a traditional Thai topical formulation. The extract was successfully standardized by its characteristic bioactive constituents derived from both botanical components. CLCS demonstrated anti-inflammatory and psoriasis-relevant biological activities”

https://www.sciencedirect.com/science/article/abs/pii/S0378874126012833?via%3Dihub

Dose Response Relationship of Medical Cannabis and Symptom Control in Patients With Pancreatic Cancer: An Analysis of the CANPAN Trial

A new analysis of the CANPAN trial found a clear dose-response relationship between THC and symptom improvement in patients with pancreatic cancer. The trial enrolled 32 cannabis-naïve patients with newly diagnosed locally advanced or metastatic pancreatic adenocarcinoma, and 23 used medical cannabis during their assigned eight-week treatment period.

Higher average daily THC doses were significantly associated with greater improvements in anxiety and insomnia. Patients receiving at least 10 mg of THC per day improved in an average of four symptoms, compared with 2.1 symptoms among patients receiving less than 10 mg per day.

The authors say these findings provide important dose-response information for future pancreatic-cancer trials, particularly for psychological symptoms and multi-symptom control. The results add to evidence from the CANPAN trial that personalized medical cannabis may have a role in managing symptoms experienced by people undergoing treatment for pancreatic cancer.

“Background: In a pilot waitlist-control randomized trial, a personalized medical cannabis intervention improved certain symptoms among patients with pancreatic cancer over 8 weeks. Longer-term and dose-response data can guide future trial design.

Methods: CANPAN enrolled 32 cannabis-naïve patients with newly diagnosed locally advanced/metastatic pancreatic adenocarcinoma (NCT06605430). Patients were randomized to early (0-8 weeks) or delayed (9-16 weeks) cannabis intervention. Primary efficacy results over the first 8 weeks were previously reported. We investigated cannabis use and patient-reported outcome (PRO) completion over 9-16 weeks, and the relationship between tetrahydrocannabinol (THC) dose and symptom efficacy.

Results: Among 32 participants, 23 (72%) used cannabis during their assigned 8-week period (12/16 in early arm and 11/16 in delayed arm). Of these, 16 (50%) had both pre-cannabis and 8-week post-cannabis initiation PRO data available. At the end of the 16-week study period, PRO data were available for 16 (50%) participants (9/16 early arm, 7/16 delayed arm). Median daily THC dose 4 weeks after starting cannabis was similar in early vs delayed arms (10 mg vs 9.3 mg). A higher average daily THC dose was associated with improvements in anxiety (r 0.52, p = 0.038) and insomnia (r 0.53, p = 0.033). A ≥ 10 mg daily THC dose (vs < 10 mg) was associated with mean improvement in 4 vs 2.1 symptoms.

Conclusions: The 50% complete data availability at 16 weeks, dose-response relationship with psychological symptoms, and threshold dose for multi-symptom efficacy will guide future trials. Similar cannabis use patterns across arms raise confidence in the waitlist-control design.”

https://pubmed.ncbi.nlm.nih.gov/42767994

https://academic.oup.com/oncolo/advance-article/doi/10.1093/oncolo/oyag374/8826188

Effectiveness and safety of cannabidiol in adult patients with epilepsy: A multicenter, retrospective study

A new multicenter study found that cannabidiol was associated with substantial seizure reductions in adults living with severe, drug-resistant forms of epilepsy. The study followed 37 adults with Dravet syndrome, Lennox–Gastaut syndrome, or tuberous sclerosis complex who received CBD for at least 12 months.

After six months, 48.6% of patients had at least a 50% reduction in seizure frequency; after 12 months, 45.9% still met that threshold. Caregivers also reported improvements in alertness, behavior, interaction, or daily functioning in 29.7% of patients, while the median number of other antiseizure medications fell from four to three.

The authors concluded that CBD was associated with “clinically meaningful seizure reduction and acceptable tolerability” in this real-world adult population. Adverse events occurred in 64.9% of patients but were mostly mild, and 81.1% remained on CBD at 12 months.

“Objective: Cannabidiol (CBD) has demonstrated promising effectiveness and tolerability as adjunctive treatment in patients with severe childhood epilepsies. This study investigated the effectiveness and tolerability of CBD in adults with a history of Dravet syndrome (DS), Lennox-Gastaut syndrome (LGS), or tuberous sclerosis complex (TSC).

Methods: This was a multicenter, retrospective, observational study in adults with diagnosis of DS, LGS or TSC who received at least 12 months of CBD treatment. Medical records were reviewed and baseline characteristics, treatment retention, seizure frequency, cognitive behavioral improvements, concomitant ASM usage, and adverse events were assessed.

Results: Thirty-seven patients (median age 25 years; 67.5% male) with diagnosis of DS, LGS or TSC received CBD for at least 12 months. The CBD median maintenance dose was 10.45 mg/kg/day (IQR 7.455 – 13.975) (median maximum dose 11 mg/kg/day); median follow-up time was 28 months (IQR 22.75-58.25). Seizure frequency was reduced by ≥50% in 48.6% of patients at 6 months and 45.9% at 12 months. No statistically significant differences in median maintenance dose were observed across seizure reduction categories. During CBD treatment, caregivers reported subjective improvements in cognition in 29.7% of patients. Treatment with CBD was significantly associated with a reduction in the median number of concomitant ASMs at the end of follow-up (4 [3, 4]) vs. 3 [3, 4] (p = 0.022). AEs occurred in 64.9% of patients and were mostly mild; 16.2% had AEs leading to treatment discontinuation.

Significance: We present a series of adult patients treated with CBD according to label. The results are similar to those described in children. CBD treatment was associated with clinically meaningful seizure reduction and acceptable tolerability in this real-world cohort of adults with drug-resistant developmental and epileptic encephalopathies. These findings support the potential role of CBD in complex adult DEE populations while highlighting the need for prospective controlled studies to better define its independent treatment effect.

Plain language summary: This study looked at the long-term use of cannabidiol (CBD) in 37 adults with Dravet syndrome, Lennox-Gastaut syndrome, or tuberous sclerosis complex. After 12 months, almost half of the patients had at least a 50% reduction in seizures. Some caregivers also reported improvements in cognition and behavior. Patients were able to reduce the number of other antiseizure medicines they were taking. Side effects were common but mostly mild, although a small number of patients stopped treatment because of them. Overall, CBD appeared effective and reasonably well tolerated, but further controlled studies are needed.”

https://pubmed.ncbi.nlm.nih.gov/42765195

“CBD has demonstrated promising effectiveness and tolerability in adult patients with a history of DS, LGS, or TSC. Treatment with CBD was associated with reductions in seizure frequency and in concomitant ASMs, which could improve treatment retention and reduce AEs. The findings support a growing body of evidence highlighting the efficacy of CBD across age groups and epilepsy etiologies in real-world clinical practice.”

https://onlinelibrary.wiley.com/doi/10.1002/epi4.70331

Evaluating the impact of cannabinoid extracts on chronic pain and quality of life in endometriosis patients – a pilot study

Women with endometriosis and chronic pelvic pain experienced significant improvements after adding a balanced oral THC cannabis extract to their existing treatment. In this prospective pilot study, 27 women completed three months of treatment, with benefits appearing within the first month and continuing through the study period.

Pain intensity fell significantly, along with the number of pain days and the need for conventional pain medicines. Use of both NSAIDs and opioid analgesics decreased, while fatigue, anxiety, central sensitization and pain-related disability also improved.

Quality of life improved across every measured EHP-30 domain, including pain, emotional well-being, work impairment, self-image and sexual relationships. The authors concluded that balanced THC cannabinoid medicines appear to be a potentially effective adjunct treatment for chronic pelvic pain and related symptoms in women with endometriosis.

“Endometriosis is a chronic gynecological disorder characterized by persistent pain and impaired quality of life, with limited effective treatment options. Emerging evidence indicates that cannabinoids may provide analgesic and symptom-relieving effects in chronic pain conditions.

This prospective single-center cohort study investigated the effects of standardized oral cannabis extracts (cannabinoid-based medicinal products, CBMPs) on pain and quality of life in women with endometriosis.

Thirty premenopausal women aged 18-45 years with confirmed endometriosis and chronic pelvic pain were enrolled; 27 completed the 3-month treatment period. Participants received oral CBMPs containing a balanced THC: CBD ratio. Pain intensity, frequency of pain episodes, analgesic use, fatigue, anxiety, central sensitization, disability, and quality of life were assessed using validated questionnaires (VAS, EHP-30, PDI, CFS, GAD-7, CSI).

Significant improvements were observed after one month of treatment, with continued benefit over three months. Pain intensity decreased markedly (p = 0.0004), accompanied by reductions in the number of pain days and analgesic use, including both NSAIDs (e.g., ibuprofen, diclofenac) and opioid analgesics (e.g., tramadol, tilidin, oxycodone) (p < 0.001). Fatigue (p = 0.0013), anxiety (p < 0.0001), central sensitization (p < 0.0001), disability (p < 0.0001), and overall quality of life (EHP-30) improved significantly.

Treatment was well tolerated; side effects were predominantly mild (severity score 1 on a 0-3 scale) and transient, occurring mainly during the titration phase and declining thereafter. Although limited by its single-center design, lack of placebo control, and short follow-up, this study provides preliminary evidence that oral CBMPs may represent a safe and effective adjunct therapy for managing pain and related symptoms in women with endometriosis. Larger randomized controlled trials are warranted to confirm these findings and establish optimal dosing strategies.”

https://pubmed.ncbi.nlm.nih.gov/42771648

“In conclusion, oral CBMPs with balanced THC: CBD ratios seem to be a safe and potentially effective adjunct therapy for chronic pelvic pain and related symptoms in women with endometriosis. By targeting both nociceptive and neuropsychological aspects of the condition, CBMPs can supplement existing pharmacological and lifestyle strategies, providing a more comprehensive approach to symptom management. These findings establish a basis for future controlled studies to refine dosing, investigate mechanisms, and assess long-term outcomes in this complex patient group.”

https://journals.plos.org/plosone/article?id=10.1371/journal.pone.0356768

Cannabinoids and therapeutic potential in neuropsychiatry

Cannabinoids are already used therapeutically in several areas of medicine, and a new review examines how that potential may extend into neuropsychiatry. The authors look beyond cannabis as a single drug, focusing instead on its individual cannabinoids and how different components may contribute to neurological and psychiatric effects.

The review highlights cannabidiol as the cannabinoid with the clearest established role in certain seizure disorders, while examining the broader literature on cannabinoids in neuropsychiatric illness. The authors argue that cannabis is more pharmacologically complicated than any one cannabinoid and that its therapeutic potential may depend on interactions among multiple plant components.

One of the review’s most important points is that combinations of cannabis components may ultimately prove more useful than isolated compounds alone. Rather than dismissing cannabis as having no medical utility in neuropsychiatry, the authors call for approaches that better investigate and use the therapeutic attributes of the plant.

“Cannabinoids have therapeutic utility in some specific areas of medicine, including as an anti-nausea adjunct for chemotherapy and as an anti-inflammatory agent, among others. However, as a therapeutic agent in neuropsychiatric conditions, the data is more limited. Cannabis itself is viewed as a recreational drug of abuse with no medical utility; however, the reality may be more complex when considering individual components of the plant.

Cannabinoid components may have some benefit as therapeutic agents in neuropsychiatry, with cannabidiol most often purported to be a therapeutic agent for some seizure disorders. However, recent studies suggest that the cannabis plant is proving to be broader and more complicated in how it delivers potential therapeutic effects. It may be that a combination of components is more effective than any one component.

This chapter reviews the medical usage of cannabinoids in neuropsychiatric illness, as reported in the literature, and proposes future approaches that may more effectively avail the attributes of this plant.”

https://pubmed.ncbi.nlm.nih.gov/42767714

“Cannabinoid treatments are carving a noteworthy niche in the pharmaceutical repertoire, offering new hope for conditions that have been historically difficult to manage, such as comorbid anxiety and epilepsy.”

https://www.sciencedirect.com/science/chapter/bookseries/abs/pii/S0074774226001303?via%3Dihub

Modulation of spatial learning and memory by cannabinoid-estrogen interaction in an AD-like cognitive impairment: The role of cannabinoid receptors and BDNF protein

A 2026 study found that a THC-standardized marijuana extract improved spatial learning and memory in an Alzheimer’s-like model of cognitive impairment. Researchers tested the extract in rats exposed to amyloid-beta, a protein closely associated with Alzheimer’s disease, and observed improvements in memory performance.

The cognitive improvements were accompanied by changes in cannabinoid receptor signaling and in BDNF, or brain-derived neurotrophic factor, a protein that supports neuron survival, brain plasticity, learning, and memory. The findings suggest that the brain’s cannabinoid system and BDNF may be involved in the neuroprotective-like effects observed with the THC-standardized extract.

The researchers also examined the interaction with estrogen and found that adding estradiol did not produce an additional synergistic improvement. As the authors concluded, “These preclinical findings suggest that a THC-standardized marijuana extract may exert neuroprotective-like effects in an AD-like cognitive impairment model.”

“Alzheimer’s disease (AD) is an increasingly prevalent neurodegenerative disorder worldwide, with women showing a higher risk of developing the disease. The decline in steroid hormones after menopause may contribute to the increased susceptibility of women to neurodegenerative conditions.

In parallel, cannabis-derived compounds have been reported to alleviate certain symptoms associated with neurological disorders. The present study was designed to investigate the effects of marijuana extract on cognitive impairment and hippocampal molecular markers in an ovariectomized AD-like rat model, and to evaluate whether co-administration with estradiol modifies these effects.

The marijuana extract used in this study was characterized by HPLC and was found to contain 8.5% Δ9-THC. AD-like cognitive impairment pathology was induced by intra-hippocampal administration of Aβ25-35 in OVX rats. Animals were treated with marijuana extract (60 mg/kg/day, corresponding to approximately 5.1 mg/kg/day Δ9-THC) either alone or in combination with 17β-estradiol (1 mg/kg every 4 days) for 28 days. Cognitive performance was evaluated using the Morris water maze (MWM). In addition, hippocampal CB1/CB2 receptor expression and BDNF protein levels were measured to examine potential molecular associations.

Our findings showed that chronic administration of the marijuana extract improved Aβ25-35-induced deficits in spatial learning and memory.

Alterations in CB1 receptor expression and BDNF levels accompanied these behavioral effects. Notably, co-treatment with estradiol did not produce a synergistic effect, suggesting a complex interaction between cannabinoid-related and estrogen-related signaling pathways.

These preclinical findings suggest that a THC-standardized marijuana extract may exert neuroprotective-like effects in an AD-like cognitive impairment model. However, because the extract was not fully phytochemically characterized and the mechanistic analyses were correlational, the results should be interpreted cautiously. Further studies are needed to clarify the underlying mechanisms and translational relevance of these findings.”

https://pubmed.ncbi.nlm.nih.gov/42756662

“In conclusion, chronic administration of THC-standardized marijuana extract improved spatial learning and memory performance in the AD-like cognitive impairment model, and these behavioral changes were accompanied by alterations in hippocampal CB1/CB2 gene expression and BDNF protein levels.”

https://www.ibroneuroreports.org/article/S2667-2421(26)00149-1/fulltext

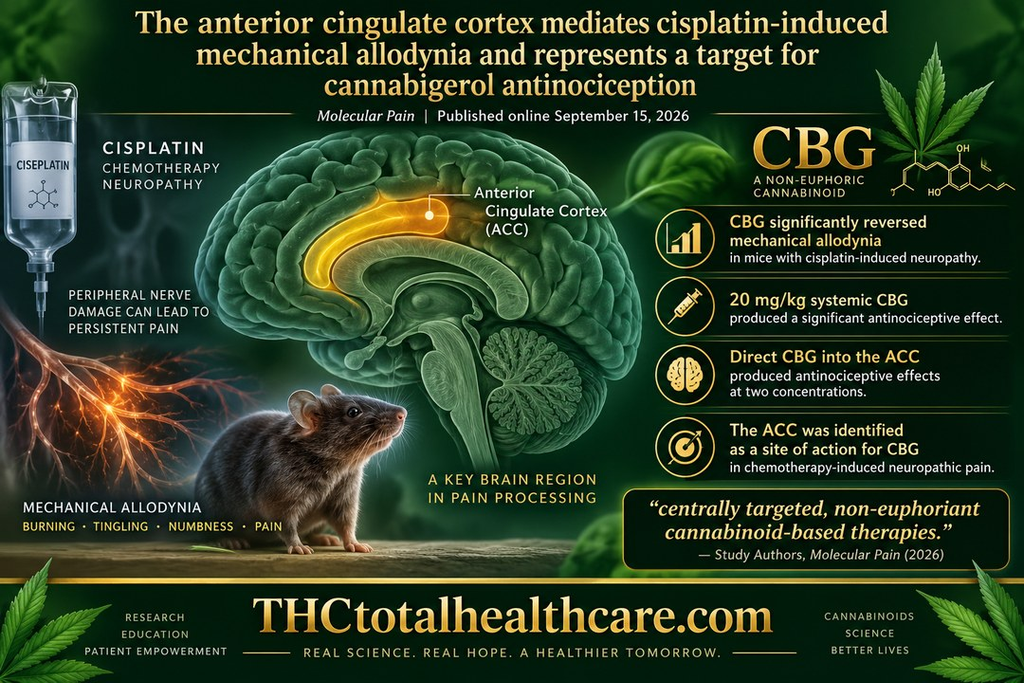
The anterior cingulate cortex mediates cisplatin-induced mechanical allodynia and represents a target for cannabigerol antinociception

Chemotherapy-induced peripheral neuropathy can cause persistent burning, tingling, numbness and pain long after cancer treatment ends. A new 2026 study investigated how the brain contributes to this neuropathic pain and whether cannabigerol (CBG), a non-euphoric cannabinoid, can reduce it.

Using a mouse model of cisplatin-induced neuropathy, researchers found that CBG significantly reversed mechanical allodynia. They also identified the anterior cingulate cortex, a brain region involved in processing pain, as an important part of the neuropathic pain response. Directly administering CBG into this region produced antinociceptive effects.

The findings suggest that CBG can act within central pain-processing circuits and identify the anterior cingulate cortex as a potential target for cannabinoid-based treatment of chemotherapy-induced neuropathic pain. The researchers say the results highlight the potential for “centrally targeted, non-euphoriant cannabinoid-based therapies.”

“Chemotherapy-induced peripheral neuropathy (CIPN) is a prevalent and debilitating consequence of cancer treatment with limited effective therapeutic options. While peripheral nerve injury is a key driver, emerging evidence suggests that maladaptive plasticity within central pain circuits, including the anterior cingulate cortex (ACC), contributes to the maintenance of neuropathic pain.

Here, we tested the hypothesis that the ACC is a critical substrate for cisplatin-induced mechanical allodynia and a target for cannabigerol (CBG)-mediated antinociception.

Adult male C57BL/6 mice received cisplatin (5 mg/kg, i.p., once weekly for four weeks) to induce CIPN. Mechanical allodynia was assessed using electronic von Frey testing.

Systemic administration of CBG (20 mg/kg, i.p.) significantly reversed mechanical allodynia in CIPN mice without affecting baseline thresholds in non-neuropathic animals, indicating a state-dependent effect. Chemogenetic inhibition of ACC neurons using hM4Di DREADDs similarly attenuated mechanical allodynia, identifying the ACC as a functionally relevant component of the CIPN pain state. To determine whether CBG acts within this circuit, bilateral intra-ACC microinjections of CBG (20 nM and 20 µM) were performed, both of which produced transient antinociceptive effects.

These findings demonstrate that the ACC contributes to the maintenance of mechanical allodynia in CIPN and establish this region as a site of action for CBG.

Together, our results support a model in which the ACC represents a convergent cortical mechanism underlying pathological pain and highlight the potential for centrally targeted, non-euphoriant cannabinoid-based therapies.”

https://pubmed.ncbi.nlm.nih.gov/42744343/

“In conclusion, this study identifies the ACC as a hub in the maintenance of mechanical allodynia in a model of CIPN. By demonstrating that chemogenetic inhibition of the ACC reverses hypersensitivity and that both systemic and local administration of CBG produce antinociceptive effects, our findings link circuit-level dysfunction to a pharmacologically targetable mechanism within this region. These results support a model in which increased or dysregulated ACC neuronal activity may represent a convergent feature of pathological pain states. Importantly, these findings demonstrate that CBG can act within the ACC to modulate mechanical allodynia. Future studies identifying the receptor targets and circuit mechanisms through which CBG acts within the ACC will be essential for refining therapeutic strategies for chronic pain.”

https://journals.sagepub.com/doi/10.1177/17448069261491110

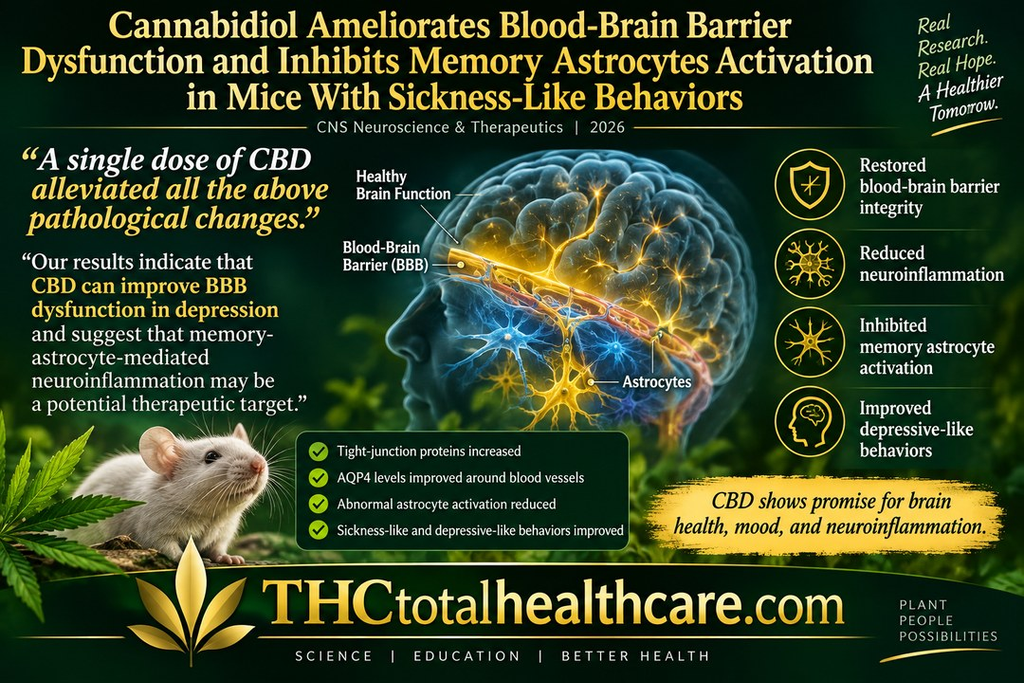
Cannabidiol Ameliorates Blood-Brain Barrier Dysfunction and Inhibits Memory Astrocytes Activation in Mice With Sickness-Like Behaviors

A new 2026 study published in CNS Neuroscience & Therapeutics found that cannabidiol (CBD) improved blood-brain barrier dysfunction, reduced neuroinflammation, and alleviated depressive-like behaviors in mice. The researchers found that sickness-like mice showed weakened blood-brain barrier integrity, reduced protective tight-junction proteins, abnormal astrocyte activation, and increased inflammation in the brain.

A single dose of CBD improved these changes, restoring important blood-brain barrier markers while reducing abnormal astrocyte activity and neuroinflammation. The researchers also identified a particularly interesting target called “memory astrocytes”—astrocytes that can respond more rapidly and strongly when exposed to a second inflammatory challenge.

The study found that CBD inhibited this memory-astrocyte-associated secondary inflammatory response, helping protect the blood-brain barrier and improve behavior. The researchers concluded that CBD may improve blood-brain barrier dysfunction associated with depression and identified memory-astrocyte-mediated neuroinflammation as a potential therapeutic target.

“Background: Blood-brain barrier (BBB) dysfunction has been increasingly implicated in the pathophysiology of depression; however, effective therapeutic strategies targeting this pathology remain limited. This study aimed to investigate the effect of cannabidiol (CBD) on improving depressive-like behaviors and BBB impairment, as well as its underlying mechanism.

Methods: Depressive-like behaviors in mice were assessed via exploratory and despair-like tests. BBB integrity was evaluated by examining tight junction protein expression in endothelial cells and AQP4 reduction from the perivascular membrane. Astrocyte activation and neuroinflammation were also measured. The therapeutic effects of a single CBD dose were examined.

Results: Mice with depressive-like phenotypes showed reduced exploratory behavior and increased despair-like behavior. In the BBB, the expression of tight junction proteins in endothelial cells was downregulated; in astrocytes, decreased AQP4 expression was observed, abnormal activation was enhanced, and neuroinflammation was elevated. A single dose of CBD alleviated all the above pathological changes. Further studies demonstrated that CBD exerted its effects by inhibiting memory astrocyte-associated secondary neuroinflammation, thereby alleviating depressive-like behaviors in mice with depressive-like phenotypes.

Conclusion: Experimental results show that CBD treatment can improve BBB dysfunction in depression and further indicates that targeted inhibition of memory astrocytes-mediated neuroinflammation may promote the treatment of depression.”

https://pubmed.ncbi.nlm.nih.gov/42747207

“Cannabidiol (CBD), a natural extract from cannabis, possesses multiple biological functions including cardioprotection, anti-inflammation, anti-cancer, anti-oxidation, and neuroprotection. Additionally, it plays indispensable roles in relieving depression and regulating BBB function]. CBD ameliorates depression by upregulating brain-derived neurotrophic factor, inhibiting neuroinflammation, alleviating oxidative stress, and modulating neurotransmitter transmission.”

https://onlinelibrary.wiley.com/doi/10.1002/cns.71168

An Ultra-Low Dose of ∆9-Tetrahydrocannabinol Alleviates Alzheimer’s Disease-Related Cognitive Impairments and Modulates TrkB Receptor Expression in a 5XFAD Mouse Model

An ultra-low dose of Δ9-THC improved Alzheimer’s disease-related cognitive impairment in 5xFAD mice, including animals treated after memory problems were already established. The study found improvements in learning and memory without relying on repeated high-dose THC exposure.

The researchers also found changes in TrkB receptor expression, a signaling pathway closely tied to brain plasticity, learning, memory, and neuronal survival. These changes suggest that THC’s effects may involve more than temporary symptom relief and may influence mechanisms connected to cognitive function.

The findings add to a growing body of preclinical research showing that very low doses of THC can produce different biological effects than higher doses, particularly in the aging and Alzheimer’s-disease brain. In this model, a single ultra-low dose was enough to improve cognitive performance and alter a key neurotrophic signaling pathway.

“Alzheimer’s disease (AD) is the most common form of dementia, but there is still no available treatment.

Δ9-tetrahydrocannabinol (THC) is emerging as a promising therapeutic agent.

Using THC in conventional high doses may have deleterious effects. Therefore, we propose to use an ultra-low dose of THC (ULD-THC). We previously published that a single injection of ULD-THC ameliorated cognitive functioning in several models of brain injuries as well as in naturally aging mice.

Here, 5xFAD AD model mice received a single treatment of ULD-THC (0.002 mg/kg) after disease onset and were examined in two separate experiments for cognitive functions, neurotropic, and inflammatory factors in the hippocampus.

We show that a single injection of ULD-THC alleviated cognitive impairments in 6- and 12-month-old 5xFAD mice. On the biochemical level, our results indicate an imbalance between the truncated TrkB receptor isoform and the full receptor, with AD mice showing a greater tendency to express the truncated receptor, and ULD-THC improved this imbalance. We also investigated the expression of three AD-related inflammatory markers and found an ameliorating effect of ULD-THC.

The current research demonstrates for the first time the beneficial effects of a single ultra-low dose of THC in a mouse model of AD after disease onset.”

https://pubmed.ncbi.nlm.nih.gov/36012711

“The current research demonstrates for the first time the beneficial effects of a single ultra-low dose of THC in a mouse model of AD after disease onset. As THC is a cheap, widely available substance already approved for use in other conditions, this research brings us closer to understanding its mechanisms and will possibly lead to new treatments.”

https://www.mdpi.com/1422-0067/23/16/9449/htm

Need this THC study explained? thcXplained.com

Δ9-Tetrahydrocannabinol treatment impairs CD8+ T cell differentiation into interferon gamma-competent CD45RO+ cells

New research published in The Journal of Pharmacology and Experimental Therapeutics shows that Δ9-tetrahydrocannabinol (THC) can alter the development of CD8+ T cells involved in inflammatory immune responses. Researchers found that THC reduced secretion of interferon gamma (IFNγ), interleukin-2 (IL-2), and tumor necrosis factor alpha (TNFα), three signaling molecules involved in immune activation and inflammation.

Rather than simply preventing cells from producing IFNγ, THC appeared to change how the T cells developed. THC reduced the differentiation of CD8+ T cells into mature CD45RO+ cells capable of secreting IFNγ. A selective CB2 receptor agonist produced similar effects, suggesting that activation of the cannabinoid CB2 receptor may play an important role in THC’s immune-modulating activity.

The researchers examined these effects partly because IFNγ-producing CD8+ T cells contribute to persistent neuroinflammation associated with HIV-associated neurocognitive disorders. They concluded that reducing CD8+ T-cell-derived IFNγ in the central nervous system may potentially improve cognitive outcomes during HIV infection, while noting that the findings may also have relevance to other inflammatory diseases involving IFNγ-producing CD8+ T cells.

“Chronic human immunodeficiency virus (HIV) infection results in a persistent state of neuroinflammation, even with combined antiretroviral therapy. Neuroinflammation contributes to pathology termed HIV-associated neurocognitive disorder, which is exacerbated by interferon gamma (IFNγ)-producing CD8+ T cells in the central nervous system.

Many people living with HIV self-report using Cannabis sativa to mitigate symptoms of chronic infection and side effects of treatment. C. sativa is composed of various phytocannabinoids, including Δ9-tetrahydrocannbinol (THC), which possesses immune-modulating properties.

This study aims to determine whether C. sativa use by people living with HIV, and specifically THC, affects IFNγ secretion by CD8+ T cells.

We found that HIV status does not influence T cell IFNγ responses, and C sativa use modestly reduces the average secretion of IFNγ by CD8+ T cells from HIV+ donors. Treatment of CD8+ T cells with THC and the selective cannabinoid receptor 2 agonist, JWH-015, reduced T-cell cytokine secretion, with THC eliciting greater suppression than cannabidiol.

These results suggest that THC treatment does not directly impair IFNγ gene expression or protein production, as determined by polymerase chain reaction and flow cytometry. However, THC treatment impaired CD8+ T cell differentiation into IFNγ-competent CD45RO+ cells.

These studies are of clinical relevance because reduction of CD8+ T-cell-derived IFNγ in the central nervous system may improve cognitive outcomes during HIV infection. Furthermore, these findings may be generalizable to other inflammatory diseases in which IFNγ-producing CD8+ T cells have been implicated.

SIGNIFICANCE STATEMENT: Δ9-Tetrahydrocannbinol (THC) treatment reduces CD8+ T cell interferon gamma (IFNγ) secretion isolated from HIV- and HIV+ individuals. THC and the selective cannabinoid receptor 2 agonist, JWH-015, both reduced CD8+ T cell secretion of IFNγ, interleukin 2, and tumor necrosis factor α, suggesting the involvement of cannabinoid receptor 2. Although THC treatment does not suppress IFNγ mRNA or protein levels, it reduces the number of IFNγ-secreting cells by impairing CD8+ T-cell differentiation into IFNγ-competent CD45RO+ cells.”

https://pubmed.ncbi.nlm.nih.gov/42748512

https://jpet.aspetjournals.org/article/S0022-3565(26)01210-3/abstract

Need this THC study explained? thcXplained.com