

Terpenes from Cannabis sativa Induce Antinociception in Mouse Chronic Neuropathic Pain via Activation of Spinal Cord Adenosine A 2A Receptors

Cannabis terpenes produced strong pain-relieving effects in mice with chemotherapy-induced peripheral neuropathy and inflammatory pain. Researchers tested geraniol, linalool, β-pinene, α-humulene and β-caryophyllene and found that, at the tested dose, their antinociceptive effects were roughly comparable to 10 mg/kg morphine or 3.2 mg/kg of the synthetic cannabinoid WIN55,212.

The terpenes also enhanced morphine’s pain-relieving effect when the two were given together at lower doses, while none of the terpenes produced reward in the conditioned-place-preference test. In the neuropathic pain model, blocking the adenosine A2A receptor significantly reduced the pain-relieving effect of every terpene tested.

Spinal-cord-specific A2A receptor knockdown further supported that mechanism, while laboratory and computer modeling suggested the terpenes can act as A2A receptor agonists. The authors concluded that Cannabis terpenes may represent potential therapeutics for chronic neuropathic pain and identified a specific receptor pathway through which that activity occurs.

“Terpenes are small hydrocarbon compounds that impart aroma and taste to many plants, including Cannabis sativa .

A number of studies have shown that terpenes can produce pain relief in various pain states in both humans and animals. However, these studies were methodologically limited and few established mechanisms of action.

In our previous work, we showed that the terpenes geraniol, linalool, β-pinene, α-humulene, and β-caryophyllene produced cannabimimetic behavioral effects via multiple receptor targets. We thus expanded this work to explore the potential antinociception and mechanism of these Cannabis terpenes in a mouse model of chronic pain.

We first tested for antinociception by injecting terpenes (200 mg/kg, IP) into male and female CD-1 mice with mouse models of chemotherapy-induced peripheral neuropathy (CIPN) or lipopolysaccharide-induced inflammatory pain, finding that the terpenes produced roughly equal antinociception to 10 mg/kg morphine or 3.2 mg/kg WIN55,212.

We further found that none of the terpenes produced reward as measured by conditioned place preference, while low doses of terpene (100 mg/kg) combined with morphine (3.2 mg/kg) produced enhanced antinociception vs either alone. We then used the adenosine A 2A receptor (A 2A R) selective antagonist istradefylline (3.2 mg/kg, IP) and spinal cord-specific CRISPR knockdown of the A 2A R to identify this receptor as the mechanism for terpene antinociception in CIPN. In vitro cAMP and binding studies and in silico modeling studies further suggested that the terpenes act as A 2A R agonists.

Together these studies identify Cannabis terpenes as potential therapeutics for chronic neuropathic pain and identify a receptor mechanism for this activity.”
https://pubmed.ncbi.nlm.nih.gov/38709489/

https://journals.lww.com/pain/abstract/10.1097/j.pain.0000000000003265~terpenes-from-cannabis-sativa-induce-antinociception-in-a?redirectionsource=fulltextview

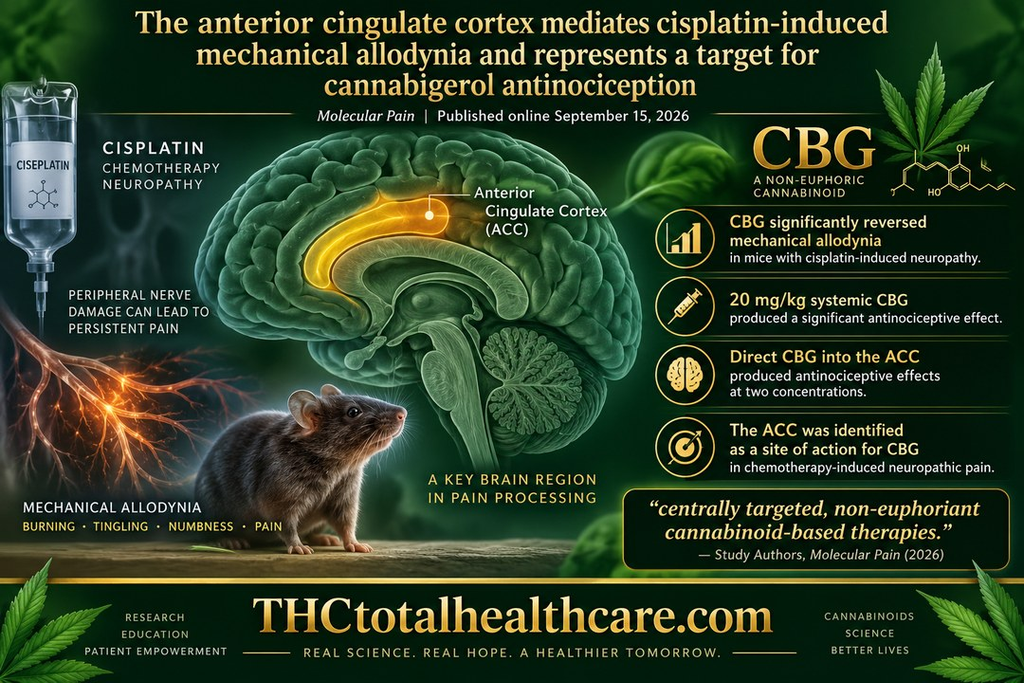
The anterior cingulate cortex mediates cisplatin-induced mechanical allodynia and represents a target for cannabigerol antinociception

Chemotherapy-induced peripheral neuropathy can cause persistent burning, tingling, numbness and pain long after cancer treatment ends. A new 2026 study investigated how the brain contributes to this neuropathic pain and whether cannabigerol (CBG), a non-euphoric cannabinoid, can reduce it.

Using a mouse model of cisplatin-induced neuropathy, researchers found that CBG significantly reversed mechanical allodynia. They also identified the anterior cingulate cortex, a brain region involved in processing pain, as an important part of the neuropathic pain response. Directly administering CBG into this region produced antinociceptive effects.

The findings suggest that CBG can act within central pain-processing circuits and identify the anterior cingulate cortex as a potential target for cannabinoid-based treatment of chemotherapy-induced neuropathic pain. The researchers say the results highlight the potential for “centrally targeted, non-euphoriant cannabinoid-based therapies.”

“Chemotherapy-induced peripheral neuropathy (CIPN) is a prevalent and debilitating consequence of cancer treatment with limited effective therapeutic options. While peripheral nerve injury is a key driver, emerging evidence suggests that maladaptive plasticity within central pain circuits, including the anterior cingulate cortex (ACC), contributes to the maintenance of neuropathic pain.

Here, we tested the hypothesis that the ACC is a critical substrate for cisplatin-induced mechanical allodynia and a target for cannabigerol (CBG)-mediated antinociception.

Adult male C57BL/6 mice received cisplatin (5 mg/kg, i.p., once weekly for four weeks) to induce CIPN. Mechanical allodynia was assessed using electronic von Frey testing.

Systemic administration of CBG (20 mg/kg, i.p.) significantly reversed mechanical allodynia in CIPN mice without affecting baseline thresholds in non-neuropathic animals, indicating a state-dependent effect. Chemogenetic inhibition of ACC neurons using hM4Di DREADDs similarly attenuated mechanical allodynia, identifying the ACC as a functionally relevant component of the CIPN pain state. To determine whether CBG acts within this circuit, bilateral intra-ACC microinjections of CBG (20 nM and 20 µM) were performed, both of which produced transient antinociceptive effects.

These findings demonstrate that the ACC contributes to the maintenance of mechanical allodynia in CIPN and establish this region as a site of action for CBG.

Together, our results support a model in which the ACC represents a convergent cortical mechanism underlying pathological pain and highlight the potential for centrally targeted, non-euphoriant cannabinoid-based therapies.”

https://pubmed.ncbi.nlm.nih.gov/42744343/

“In conclusion, this study identifies the ACC as a hub in the maintenance of mechanical allodynia in a model of CIPN. By demonstrating that chemogenetic inhibition of the ACC reverses hypersensitivity and that both systemic and local administration of CBG produce antinociceptive effects, our findings link circuit-level dysfunction to a pharmacologically targetable mechanism within this region. These results support a model in which increased or dysregulated ACC neuronal activity may represent a convergent feature of pathological pain states. Importantly, these findings demonstrate that CBG can act within the ACC to modulate mechanical allodynia. Future studies identifying the receptor targets and circuit mechanisms through which CBG acts within the ACC will be essential for refining therapeutic strategies for chronic pain.”

https://journals.sagepub.com/doi/10.1177/17448069261491110