A 2026 study found that a THC-standardized marijuana extract improved spatial learning and memory in an Alzheimer’s-like model of cognitive impairment. Researchers tested the extract in rats exposed to amyloid-beta, a protein closely associated with Alzheimer’s disease, and observed improvements in memory performance.
The cognitive improvements were accompanied by changes in cannabinoid receptor signaling and in BDNF, or brain-derived neurotrophic factor, a protein that supports neuron survival, brain plasticity, learning, and memory. The findings suggest that the brain’s cannabinoid system and BDNF may be involved in the neuroprotective-like effects observed with the THC-standardized extract.
The researchers also examined the interaction with estrogen and found that adding estradiol did not produce an additional synergistic improvement. As the authors concluded, “These preclinical findings suggest that a THC-standardized marijuana extract may exert neuroprotective-like effects in an AD-like cognitive impairment model.”
“Alzheimer’s disease (AD) is an increasingly prevalent neurodegenerative disorder worldwide, with women showing a higher risk of developing the disease. The decline in steroid hormones after menopause may contribute to the increased susceptibility of women to neurodegenerative conditions.
In parallel, cannabis-derived compounds have been reported to alleviate certain symptoms associated with neurological disorders. The present study was designed to investigate the effects of marijuana extract on cognitive impairment and hippocampal molecular markers in an ovariectomized AD-like rat model, and to evaluate whether co-administration with estradiol modifies these effects.
The marijuana extract used in this study was characterized by HPLC and was found to contain 8.5% Δ9-THC. AD-like cognitive impairment pathology was induced by intra-hippocampal administration of Aβ25-35 in OVX rats. Animals were treated with marijuana extract (60 mg/kg/day, corresponding to approximately 5.1 mg/kg/day Δ9-THC) either alone or in combination with 17β-estradiol (1 mg/kg every 4 days) for 28 days. Cognitive performance was evaluated using the Morris water maze (MWM). In addition, hippocampal CB1/CB2 receptor expression and BDNF protein levels were measured to examine potential molecular associations.
Our findings showed that chronic administration of the marijuana extract improved Aβ25-35-induced deficits in spatial learning and memory.
Alterations in CB1 receptor expression and BDNF levels accompanied these behavioral effects. Notably, co-treatment with estradiol did not produce a synergistic effect, suggesting a complex interaction between cannabinoid-related and estrogen-related signaling pathways.
These preclinical findings suggest that a THC-standardized marijuana extract may exert neuroprotective-like effects in an AD-like cognitive impairment model. However, because the extract was not fully phytochemically characterized and the mechanistic analyses were correlational, the results should be interpreted cautiously. Further studies are needed to clarify the underlying mechanisms and translational relevance of these findings.”
“In conclusion, chronic administration of THC-standardized marijuana extract improved spatial learning and memory performance in the AD-like cognitive impairment model, and these behavioral changes were accompanied by alterations in hippocampal CB1/CB2 gene expression and BDNF protein levels.”
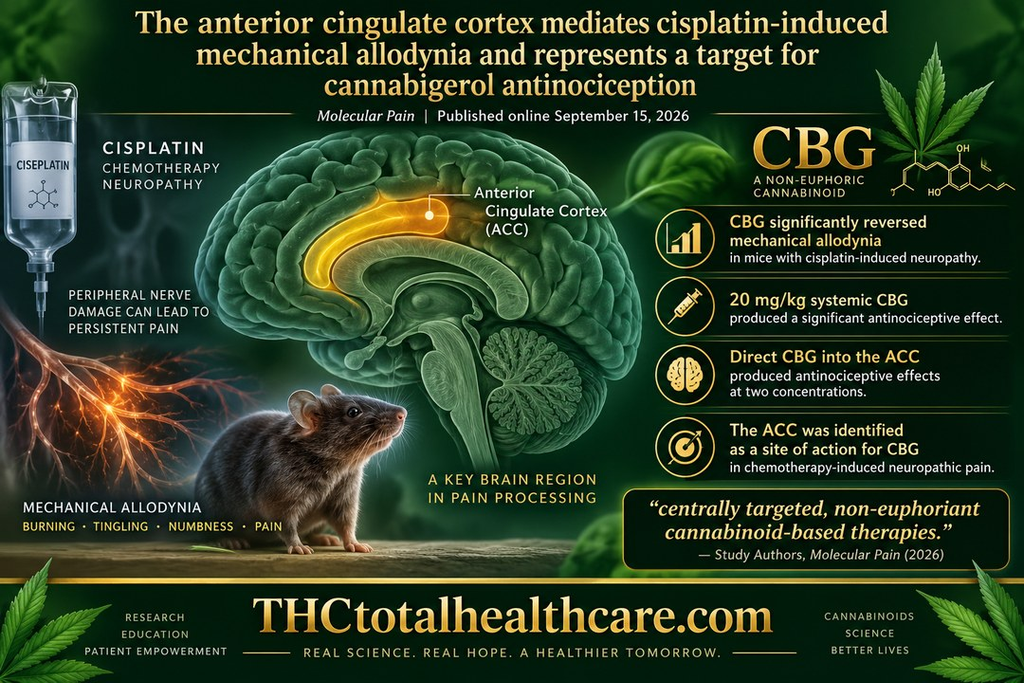
Chemotherapy-induced peripheral neuropathy can cause persistent burning, tingling, numbness and pain long after cancer treatment ends. A new 2026 study investigated how the brain contributes to this neuropathic pain and whether cannabigerol (CBG), a non-euphoric cannabinoid, can reduce it.
Using a mouse model of cisplatin-induced neuropathy, researchers found that CBG significantly reversed mechanical allodynia. They also identified the anterior cingulate cortex, a brain region involved in processing pain, as an important part of the neuropathic pain response. Directly administering CBG into this region produced antinociceptive effects.
The findings suggest that CBG can act within central pain-processing circuits and identify the anterior cingulate cortex as a potential target for cannabinoid-based treatment of chemotherapy-induced neuropathic pain. The researchers say the results highlight the potential for “centrally targeted, non-euphoriant cannabinoid-based therapies.”
“Chemotherapy-induced peripheral neuropathy (CIPN) is a prevalent and debilitating consequence of cancer treatment with limited effective therapeutic options. While peripheral nerve injury is a key driver, emerging evidence suggests that maladaptive plasticity within central pain circuits, including the anterior cingulate cortex (ACC), contributes to the maintenance of neuropathic pain.
Here, we tested the hypothesis that the ACC is a critical substrate for cisplatin-induced mechanical allodynia and a target for cannabigerol (CBG)-mediated antinociception.
Adult male C57BL/6 mice received cisplatin (5 mg/kg, i.p., once weekly for four weeks) to induce CIPN. Mechanical allodynia was assessed using electronic von Frey testing.
Systemic administration of CBG (20 mg/kg, i.p.) significantly reversed mechanical allodynia in CIPN mice without affecting baseline thresholds in non-neuropathic animals, indicating a state-dependent effect. Chemogenetic inhibition of ACC neurons using hM4Di DREADDs similarly attenuated mechanical allodynia, identifying the ACC as a functionally relevant component of the CIPN pain state. To determine whether CBG acts within this circuit, bilateral intra-ACC microinjections of CBG (20 nM and 20 µM) were performed, both of which produced transient antinociceptive effects.
These findings demonstrate that the ACC contributes to the maintenance of mechanical allodynia in CIPN and establish this region as a site of action for CBG.
Together, our results support a model in which the ACC represents a convergent cortical mechanism underlying pathological pain and highlight the potential for centrally targeted, non-euphoriant cannabinoid-based therapies.”
“In conclusion, this study identifies the ACC as a hub in the maintenance of mechanical allodynia in a model of CIPN. By demonstrating that chemogenetic inhibition of the ACC reverses hypersensitivity and that both systemic and local administration of CBG produce antinociceptive effects, our findings link circuit-level dysfunction to a pharmacologically targetable mechanism within this region. These results support a model in which increased or dysregulated ACC neuronal activity may represent a convergent feature of pathological pain states. Importantly, these findings demonstrate that CBG can act within the ACC to modulate mechanical allodynia. Future studies identifying the receptor targets and circuit mechanisms through which CBG acts within the ACC will be essential for refining therapeutic strategies for chronic pain.”
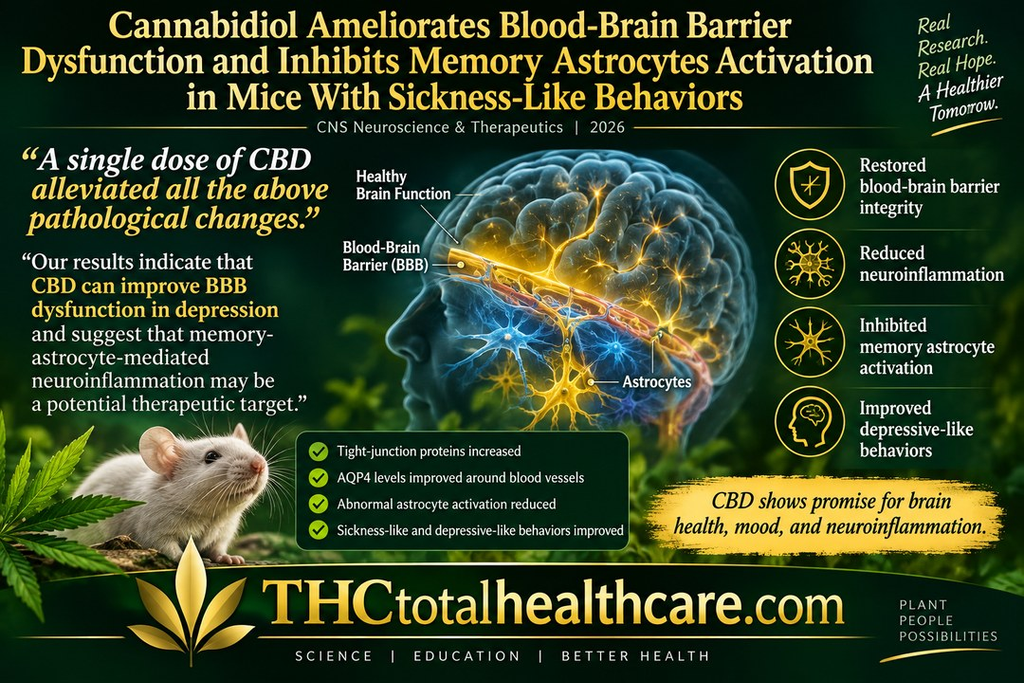
A new 2026 study published in CNS Neuroscience & Therapeutics found that cannabidiol (CBD) improved blood-brain barrier dysfunction, reduced neuroinflammation, and alleviated depressive-like behaviors in mice. The researchers found that sickness-like mice showed weakened blood-brain barrier integrity, reduced protective tight-junction proteins, abnormal astrocyte activation, and increased inflammation in the brain.
A single dose of CBD improved these changes, restoring important blood-brain barrier markers while reducing abnormal astrocyte activity and neuroinflammation. The researchers also identified a particularly interesting target called “memory astrocytes”—astrocytes that can respond more rapidly and strongly when exposed to a second inflammatory challenge.
The study found that CBD inhibited this memory-astrocyte-associated secondary inflammatory response, helping protect the blood-brain barrier and improve behavior. The researchers concluded that CBD may improve blood-brain barrier dysfunction associated with depression and identified memory-astrocyte-mediated neuroinflammation as a potential therapeutic target.
“Background: Blood-brain barrier (BBB) dysfunction has been increasingly implicated in the pathophysiology of depression; however, effective therapeutic strategies targeting this pathology remain limited. This study aimed to investigate the effect of cannabidiol (CBD) on improving depressive-like behaviors and BBB impairment, as well as its underlying mechanism.
Methods: Depressive-like behaviors in mice were assessed via exploratory and despair-like tests. BBB integrity was evaluated by examining tight junction protein expression in endothelial cells and AQP4 reduction from the perivascular membrane. Astrocyte activation and neuroinflammation were also measured. The therapeutic effects of a single CBD dose were examined.
Results: Mice with depressive-like phenotypes showed reduced exploratory behavior and increased despair-like behavior. In the BBB, the expression of tight junction proteins in endothelial cells was downregulated; in astrocytes, decreased AQP4 expression was observed, abnormal activation was enhanced, and neuroinflammation was elevated. A single dose of CBD alleviated all the above pathological changes. Further studies demonstrated that CBD exerted its effects by inhibiting memory astrocyte-associated secondary neuroinflammation, thereby alleviating depressive-like behaviors in mice with depressive-like phenotypes.
Conclusion: Experimental results show that CBD treatment can improve BBB dysfunction in depression and further indicates that targeted inhibition of memory astrocytes-mediated neuroinflammation may promote the treatment of depression.”
“Cannabidiol (CBD), a natural extract from cannabis, possesses multiple biological functions including cardioprotection, anti-inflammation, anti-cancer, anti-oxidation, and neuroprotection. Additionally, it plays indispensable roles in relieving depression and regulating BBB function]. CBD ameliorates depression by upregulating brain-derived neurotrophic factor, inhibiting neuroinflammation, alleviating oxidative stress, and modulating neurotransmitter transmission.”
New research published in The Journal of Pharmacology and Experimental Therapeutics shows that Δ9-tetrahydrocannabinol (THC) can alter the development of CD8+ T cells involved in inflammatory immune responses. Researchers found that THC reduced secretion of interferon gamma (IFNγ), interleukin-2 (IL-2), and tumor necrosis factor alpha (TNFα), three signaling molecules involved in immune activation and inflammation.
Rather than simply preventing cells from producing IFNγ, THC appeared to change how the T cells developed. THC reduced the differentiation of CD8+ T cells into mature CD45RO+ cells capable of secreting IFNγ. A selective CB2 receptor agonist produced similar effects, suggesting that activation of the cannabinoid CB2 receptor may play an important role in THC’s immune-modulating activity.
The researchers examined these effects partly because IFNγ-producing CD8+ T cells contribute to persistent neuroinflammation associated with HIV-associated neurocognitive disorders. They concluded that reducing CD8+ T-cell-derived IFNγ in the central nervous system may potentially improve cognitive outcomes during HIV infection, while noting that the findings may also have relevance to other inflammatory diseases involving IFNγ-producing CD8+ T cells.
“Chronic human immunodeficiency virus (HIV) infection results in a persistent state of neuroinflammation, even with combined antiretroviral therapy. Neuroinflammation contributes to pathology termed HIV-associated neurocognitive disorder, which is exacerbated by interferon gamma (IFNγ)-producing CD8+ T cells in the central nervous system.
Many people living with HIV self-report using Cannabis sativa to mitigate symptoms of chronic infection and side effects of treatment. C. sativa is composed of various phytocannabinoids, including Δ9-tetrahydrocannbinol (THC), which possesses immune-modulating properties.
This study aims to determine whether C. sativa use by people living with HIV, and specifically THC, affects IFNγ secretion by CD8+ T cells.
We found that HIV status does not influence T cell IFNγ responses, and C sativa use modestly reduces the average secretion of IFNγ by CD8+ T cells from HIV+ donors. Treatment of CD8+ T cells with THC and the selective cannabinoid receptor 2 agonist, JWH-015, reduced T-cell cytokine secretion, with THC eliciting greater suppression than cannabidiol.
These results suggest that THC treatment does not directly impair IFNγ gene expression or protein production, as determined by polymerase chain reaction and flow cytometry. However, THC treatment impaired CD8+ T cell differentiation into IFNγ-competent CD45RO+ cells.
These studies are of clinical relevance because reduction of CD8+ T-cell-derived IFNγ in the central nervous system may improve cognitive outcomes during HIV infection. Furthermore, these findings may be generalizable to other inflammatory diseases in which IFNγ-producing CD8+ T cells have been implicated.
SIGNIFICANCE STATEMENT: Δ9-Tetrahydrocannbinol (THC) treatment reduces CD8+ T cell interferon gamma (IFNγ) secretion isolated from HIV- and HIV+ individuals. THC and the selective cannabinoid receptor 2 agonist, JWH-015, both reduced CD8+ T cell secretion of IFNγ, interleukin 2, and tumor necrosis factor α, suggesting the involvement of cannabinoid receptor 2. Although THC treatment does not suppress IFNγ mRNA or protein levels, it reduces the number of IFNγ-secreting cells by impairing CD8+ T-cell differentiation into IFNγ-competent CD45RO+ cells.”
The first time I heard Olivia Newton-John’s voice on the radio, I thought she might be an angel.
Decades later, when I heard that same voice on the news championing a controversial cause close to my heart, I felt I had been right.
In May 2017, before I knew her breast cancer had returned, I received an instant message from someone claiming to be Olivia Newton-John. The message encouraged me to keep doing what I was doing — sharing science — and echoed a phrase I had been posting for years:
“Thank you for sharing.”
I remember what happened next because I watched it unfold in real time.
The world learned that Olivia Newton-John’s breast cancer had returned and metastasized to her sacrum. By June, I was reading reports that she was using cannabis oil. By September, she was talking about cannabis openly.
And not timidly.
In an Australian 60 Minutes interview, Olivia called cannabis a “magical, miracle plant.” Days later, on American television, she called it “a healing plant.”
She said it helped her pain. She discussed inflammation. Over the following years, she would talk about cannabis helping her sleep and anxiety. She credited her husband, John Easterling, with growing cannabis and preparing tinctures specifically for her. She later said cannabis helped her wean herself off morphine.
“I couldn’t have got through this time without it,” she said in 2019.
Yet I remember watching another story develop alongside hers.
Olivia was telling the public how well she was doing, how important cannabis had become to her and how determined she was to live.
Much of the news coverage, however, increasingly felt like a countdown toward her death.
That became especially frustrating in 2018.
Olivia revealed that the cancer she had publicly disclosed in 2017 was actually her third experience with breast cancer. Her first diagnosis had come in 1992. She had experienced another recurrence in 2013 but chose to keep it private.
That was significant new information.
But it was not a new recurrence in 2018.
Nevertheless, headlines appeared announcing that Olivia Newton-John’s cancer had “returned for a third time.” To someone encountering the story casually, it could sound as though she had suffered another fresh setback.
The individual facts were technically true but the overall impression was misleading.
At the same time some headlines were emphasizing another “cancer battle,” Olivia was appearing publicly, participating in her Wellness Walk, talking about “winning over” cancer and telling interviewers she was doing well.
One source close to her pushed back against reports suggesting her condition had suddenly worsened, saying the information being reported was the same diagnosis she had disclosed the previous year.
I wanted to call attention to that disconnect then.
I did not have the ability to assemble years of interviews, headlines and contemporaneous reporting the way I can now.
But I remembered it.
And when the chronology is reconstructed, Olivia Newton-John’s story looks different.
She was never simply a celebrity who used marijuana.
Her relationship with cannabis became part of a much larger philosophy of cancer care.
Olivia had embraced complementary approaches since her first cancer diagnosis. She used conventional medicine, too. That point matters because her story is sometimes reduced to a false choice between cannabis and oncology.
Her approach was integrative.
Over the years she underwent surgery, chemotherapy, radiation, hormone therapy and other medical treatments while also using meditation, herbs, supplements, homeopathy, acupuncture, cannabis and other wellness practices.
She described treatment decisions as deeply personal.
Her husband, John Easterling, added another dimension.
Long before cannabis became central to their public story, Easterling had spent years studying plants and working with botanical medicine. Newton-John called him her “plant medicine man.”
The two seemed almost destined to find each other: a woman already drawn to holistic healing and a man who had devoted much of his life to medicinal plants.
By the time Newton-John was living with metastatic disease, Easterling was cultivating different cannabis strains at their California home and making tinctures for her.
Olivia said she did not like feeling intoxicated.
What she repeatedly emphasized was relief.
“If I don’t take the cannabis, I can feel the pain so I know it’s working,” she told 60 Minutes reporter Liz Hayes.
She called herself “incredibly pro cannabis.”
Her advocacy eventually moved beyond her own use.
“My dream is that it will be available to all the cancer patients or people going through cancer or any kind of disease that causes pain,” she said.
She talked about parents facing prosecution while seeking cannabis for children with epilepsy. She challenged the stigma surrounding the plant. She argued that patients deserved the right to try it.
And sometimes she went further than cautious symptom language.
She talked about cannabis and healing. She said research was examining the plant “not just for pain but to cure things.” She said she believed medicinal cannabis could play a major role in defeating cancer.
Those statements should be understood for what they were: the beliefs and hopes of a patient and advocate, not the results of a randomized clinical trial.
But that is precisely where her story becomes particularly important.
She did not stop at belief.
She wanted research.
That may be the part of her cannabis legacy most worth remembering.
Olivia spent years raising money and lending her name to what became the Olivia Newton-John Cancer Wellness & Research Centre in Melbourne, Australia. She insisted that “wellness” be part of the institution because she believed cancer care should treat the whole person, not merely the tumor.
Her later foundation explicitly sought to fund research into plant medicine.
And today, that idea is becoming reality.
The RESONANCE trial is studying medicinal cannabis in people with advanced cancer, examining symptoms, quality of life, tolerability and adverse effects.
The research represents something Olivia repeatedly called for: move beyond stigma, beyond anecdotes and beyond political arguments, and actually study what cannabis can and cannot do for patients.
That is why the timing of this story matters.
Olivia Newton-John would have turned 78 on September 26.
The medicinal-cannabis trial her advocacy helped inspire is actively recruiting.
October is Breast Cancer Awareness Month.
And on October 4, supporters will gather for the final Olivia’s Walk for Wellness.
The walk is ending.
The research is not.
Neither should our examination of the story Olivia Newton-John was trying to tell us.
For years, Olivia told interviewers that cannabis helped her through severe pain, improved her sleep, aided her quality of life and changed the way she thought about a plant she once approached nervously.
Then she used her celebrity to ask why other patients could not have the same opportunity.
Finally, she tried to move the conversation from testimony to action.
I watched her journey unfold online.
What frustrated me then was seeing a woman talking about healing, hope and the wonderful things she believed this plant was doing for her, while the public narrative so often seemed fixated on how close she was to dying.
What strikes me now that she is gone is what she left behind.
The headlines eventually stopped.
The interviews remain.
The cancer center remains.
The science continues.
Can cannabis fight cancer?
She believed it could.
Decades of laboratory and preclinical research have given scientists reason to keep asking the question Olivia Newton-John wanted answered.
The research she called for is being done.
Perhaps that is the most fitting way to remember her as her birthday approaches, as supporters prepare for the final Walk for Wellness.
Not merely as a celebrity who had cancer and used cannabis.
But as someone who turned what she learned from living with it for 30 years into a legacy that will walk on.
A 2026 study published in PLOS ONE found that hemp leaf extracts were both toxic and repellent to adult female Aedes aegypti mosquitoes, the species responsible for transmitting diseases including yellow fever, dengue and chikungunya. Researchers observed dose-dependent mosquito mortality within 24 hours after direct exposure to the hemp extract.
The hemp extract also reduced blood-feeding and produced strong contact-repellent effects. Importantly, isolated cannabidiol (CBD) did not reproduce the full activity of the whole extract, suggesting that other cannabinoids, terpenes or additional hemp compounds may contribute to the effect.
The findings add to growing research into hemp-derived compounds as potential plant-based tools for insect and mosquito control. The authors concluded that hemp leaf extracts showed both topical toxicity and repellency against yellow fever mosquitoes, with effects that could not be duplicated by CBD alone.
“Hemp (Cannabis sativa) derived products have emerged as potential sources of novel biopesticides.
We recently demonstrated that a hemp leaf extract was toxic to larvae of the yellow fever mosquito Aedes aegypti, and that cannabidiol (CBD) was the primary larvicidal component of the extract.
Here we evaluated the toxic and repellent effects of a hemp leaf extract and CBD against adult female Ae. aegypti.
Toxicity was assessed using an acute topical assay in which mosquitoes received a 500 nL application to the thorax and mortality was recorded at 24 h. Repellency was then evaluated using two complementary bioassays: (i) a no-choice membrane blood-feeding assay to quantify feeding deterrence, and (ii) a mosquito airborne repellency test (MART) to assess spatial repellency.
Topical application of CBD-rich hemp leaf extract induced dose-dependent mortality in adult Ae. aegypti with a LD50 of 22.13 µg/mosquito at 24 h. When CBD isolate was tested at its equivalent doses in the extract, it caused significantly lower mortality than the hemp extract.
In the membrane blood-feeding repellency assay, the hemp leaf extract repelled mosquitoes in a dose-dependent manner, whereas CBD produced weaker effects even at higher equivalent doses. In the MART assay, the hemp extract did not elicit spatial repellency, suggesting low volatility of the repellent compounds.
Taken together, our results demonstrate that CBD does not fully explain the adulticidal or repellent effects of the CBD-rich hemp leaf extract against adult female Ae. aegypti suggesting that other compounds contribute to the bioactivity of hemp leaf extracts against adult female mosquitoes.”
“This study demonstrates that hemp leaf extracts exhibit topical toxicity and repellency against the yellow fever mosquito, Ae. aegypti, and that these effects cannot be duplicated by CBD alone. The greater toxicity of the hemp leaf extract compared to the CBD isolate suggests important contributions by other compounds in the extracts. When repellency of the extract or CBD was evaluated, mosquitoes were only repelled when direct contact with the treated surface was allowed. Nevertheless, the hemp leaf extract was more effective than the CBD isolate, again pointing to the involvement of other compounds in adult repellency.
Our findings advance our understanding of the potential uses of hemp and CBD against adult female Ae. aegypti. Identifying the additional components of the leaf extract that contribute to toxicity and repellency in adult female mosquitoes will be essential for evaluating the potential of hemp-based products in integrated mosquito management strategies. In addition, future research evaluating the human and environmental safety of using hemp-derived products as biopesticides is needed.”
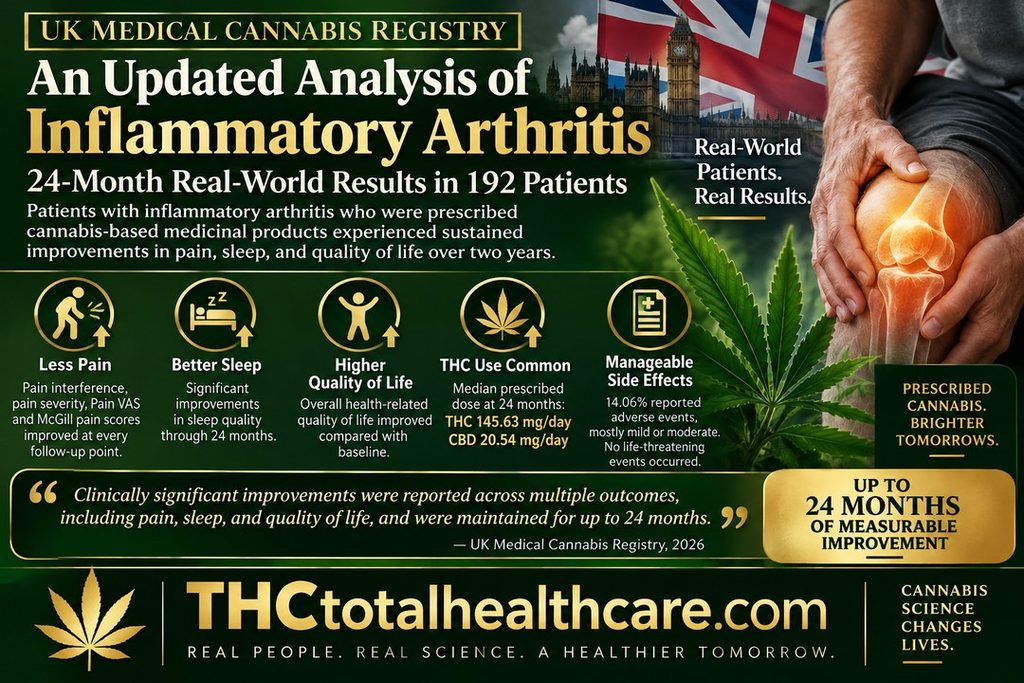
A new analysis from the UK Medical Cannabis Registry reports sustained improvements in pain, sleep, and health-related quality of life among patients with inflammatory arthritis who were prescribed cannabis-based medicinal products.
The study followed 192 patients for up to 24 months. Improvements were reported across multiple pain measures at every follow-up point, including pain severity, pain interference, and overall pain scores. Sleep quality and general quality of life also improved compared with baseline.
Notably, many patients were prescribed THC-containing products, including dried cannabis flower and oils. The findings add long-term real-world evidence that prescribed cannabis medicines may help some people living with inflammatory arthritis.
“Aim: Cannabis-based medicinal products (CBMPs) are an emerging therapeutic option for pain in inflammatory arthritis, yet clinical evidence remains limited. This study aimed to evaluate changes in pain-specific and general health-related outcomes in patients with inflammatory arthritis treated with CBMPs and to characterize the safety profile by examining the incidence and nature of adverse events.
Methods: Patients treated with CBMPs for inflammatory arthritis-associated pain for ⩾24 months were identified from the UK Medical Cannabis Registry. Primary outcomes included changes in patient-reported measures: Brief Pain Inventory (BPI), Pain Visual Analogue Scale (Pain VAS), Short-Form McGill Pain Questionnaire 2 (SF-MPQ-2), EuroQol 5-dimension 5-level (EQ-5D-5L), Generalized Anxiety Disorder-7 (GAD-7), and Single-Item Sleep Quality Scale (SQS) at 1, 3, 6, 12, 18, and 24 months vs baseline. Adverse events were recorded and analysed. Statistical significance was set at P < .050.
Results: A total of 192 patients met inclusion criteria. The CBMP initiation was associated with improvements in BPI Interference, BPI Severity, Pain VAS, SF-MPQ-2, SQS, and EQ-5D-5L index values at all follow-up time points (P < .010) and in GAD-7 scores up to 3 months (P < .001). Twenty-seven patients (14.06%) reported 296 adverse events: 126 (42.57%) mild, 132 (44.59%) moderate, and 38 (12.84%) severe. No life-threatening events occurred.
Conclusion: The CBMP therapy was associated with reductions in pain and improvements in health-related quality of life among individuals with inflammatory arthritis. Although causality cannot be inferred from this observational design, these findings support the need for randomized controlled trials to determine the efficacy of CBMPs for inflammatory arthritis-related pain.”
“Overall, results of this study demonstrate reductions in pain severity and improvements in HRQoL for patients receiving CBMP treatment for chronic pain linked to inflammatory arthritis over a period of 24 months of follow-up. The CBMPs were generally well-tolerated, although the risk of AE and individual responses should be considered before commencing CBMP treatment.”
Hemp may have value far beyond its traditional uses. A 2026 study examining hemp leaves and inflorescences found that both plant parts contain bioactive compounds with potential nutritional value, while extracts from the plants also demonstrated antibacterial activity against several important bacterial species.
Researchers found that hemp flowers were especially rich in cannabinoids and terpenes, while the leaves offered a favorable fatty-acid profile. In laboratory testing, hemp extracts showed activity against Staphylococcus aureus, Escherichia coli, and Pseudomonas aeruginosa, highlighting another potential use for compounds naturally produced by the cannabis plant.
The researchers suggest that hemp leaves and flowers deserve further investigation as functional ingredients in canine nutrition. The findings add to growing evidence that parts of the cannabis plant often treated as agricultural byproducts may contain valuable nutritional and biologically active compounds.
“Hemp (Cannabis sativa L.) inflorescences have been extensively characterized for their bioactive compounds, whereas less information is available on hemp leaves despite their potential as a source of nutrients and phytochemicals.
This study compared leaves and inflorescences of four organically grown hemp cultivars (Finola, Futura 75, Dioica, and Kompolti) in terms of cannabinoid, terpene, and fatty acid profiles, lipid quality indices, and in vitro antibacterial activity.
Antibacterial activity against Staphylococcus aureus, Escherichia coli, and Pseudomonas aeruginosa was evaluated using MIC, MBC, and time-kill assays. Total cannabinoid content was approximately 2.7-fold higher in inflorescences than in leaves, which were also generally richer in terpenes. Leaves showed a more favorable fatty acid profile, with higher n-3 polyunsaturated fatty acid proportions and a lower n-6/n-3 ratio.
All extracts exhibited antibacterial activity. Among the tested bacteria, S. aureus was the most susceptible to the hemp extracts, with both growth inhibition and bactericidal activity observed at the lowest tested concentration (MIC/MBC = 0.005%), compared with 0.625% for E. coli and 1.25-2.5% for P. aeruginosa, depending on the extract. Finola and Kompolti inflorescence extracts showed the fastest bactericidal activity against S. aureus.
These findings demonstrate distinct and complementary characteristics of hemp leaves and inflorescences and provide a basis for further investigation of their potential relevance to canine nutrition.”
“The pet food industry is increasingly looking for natural ingredients that can improve both the nutritional value and microbiological safety of dog diets while making better use of agricultural resources. Industrial hemp cultivation generates large amounts of leaves that are often underutilized, although they contain valuable natural compounds. This study compared hemp leaves and inflorescences from four industrial hemp cultivars to determine whether these plant materials could be useful in canine nutrition.
The results showed that leaves provide a favorable fatty acid profile, whereas inflorescences are richer in naturally occurring plant compounds such as cannabinoids and terpenes. Extracts from both plant parts also inhibited the growth of bacteria under laboratory conditions. These findings suggest that different hemp plant parts may have complementary roles as functional ingredients in dog foods while supporting more sustainable use of hemp biomass. Further studies in complete diets and feeding trials are needed before practical application.”
The science of the endocannabinoid system has advanced dramatically, but cannabinoid-based medicine is still being held back by forces outside the laboratory. This new Clinical Therapeutics commentary argues that the biological understanding of the endocannabinoid system is no longer the main limiting factor. The larger barriers are now policy, regulation, funding, access, and stigma.
According to the authors, restrictive and fragmented rules make cannabinoid research harder to conduct, while limited access to standardized products complicates rigorous clinical trials. At the same time, stigma within medicine can discourage research, education, prescribing, and open discussion with patients.
The message is simple: the remaining evidence gaps are not purely scientific. They are also structural. If cannabinoid-based medicine is going to move forward, policy and medical culture will have to catch up with what researchers already understand about the endocannabinoid system.
“Purpose: To examine whether the persistent gap between the extensive mechanistic knowledge of the Endocannabinoid System (ECS) and the limited number of high-quality randomized clinical trials of cannabinoid-based therapies primarily reflects scientific uncertainty or, instead, structural regulatory, economic, and social barriers.
Methods: This commentary critically synthesizes historical, regulatory, and contemporary evidence on cannabinoid research, integrating data from regulatory documents, international policy reports, clinical and observational studies, systematic reviews, and qualitative investigations. Particular emphasis is placed on barriers affecting access to standardized products, conduct of randomized clinical trials, public funding, product standardization, and healthcare professionals’ perceptions.
Findings: Although the ECS has been extensively characterized for more than three decades and cannabinoids demonstrate plausible pharmacological mechanisms across multiple therapeutic areas, clinical translation remains disproportionately limited. Persistent regulatory restrictions, inherited from prohibition policies, continue to delay access to standardized research material, increase the cost and complexity of clinical trials, and shift evidence generation toward observational designs. Regulatory fragmentation further compromises product standardization and study reproducibility, whereas persistent social and professional stigma reduces research activity, medical education, prescribing confidence, and patient disclosure, perpetuating a self-reinforcing cycle between limited evidence generation and clinical distrust.
Implications: The principal obstacle to cannabinoid-based medicine is no longer the biological understanding of the ECS but the structural environment surrounding cannabinoid research. Progress toward evidence-based clinical implementation will depend on regulatory harmonization, greater public investment in randomized clinical research, standardized pharmaceutical-quality products, and educational initiatives capable of reducing stigma among healthcare professionals. Recognizing the structural rather than scientific origin of the evidence gap is essential for informing future research priorities, editorial policies, and international regulatory strategies.”
“The ECS is no longer the main obstacle to cannabinoid therapeutics. Stigma and regulation continue to delay clinical translation. Standardized clinical research requires international regulatory reform. Medical education is crucial for evidence-based cannabinoid therapies.”
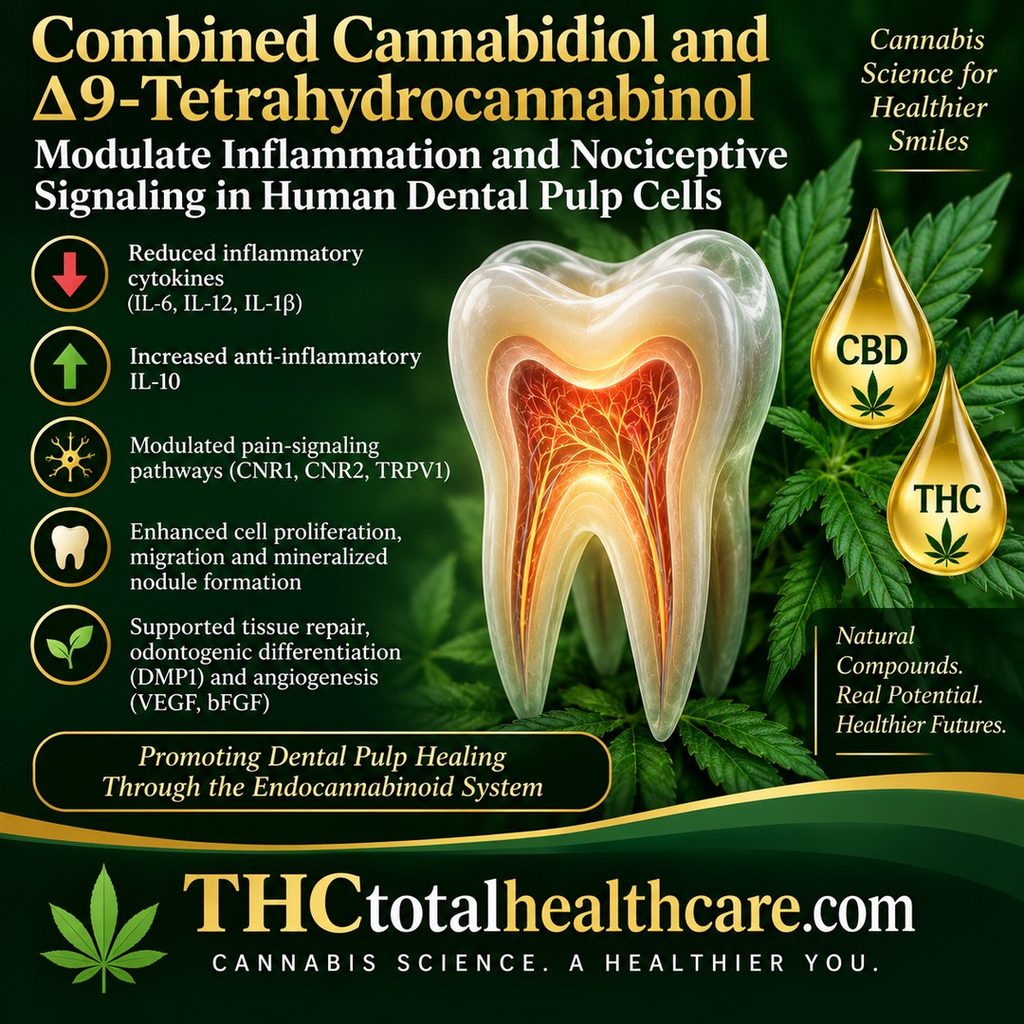
A new study using human dental pulp cells found that combining cannabidiol (CBD) and Δ9-tetrahydrocannabinol (THC) produced stronger anti-inflammatory effects than either cannabinoid alone. The combination reduced the pro-inflammatory cytokines IL-6, IL-12, and IL-1β while increasing the anti-inflammatory cytokine IL-10.
CBD and THC together also influenced important pathways involved in pain signaling and healing. Researchers reported increased expression of the cannabinoid receptors CNR1 and CNR2, modulation of TRPV1, and enhanced cell proliferation and migration. The combination also promoted mineralized nodule formation and increased markers associated with odontogenic differentiation and new blood-vessel formation.
The researchers concluded that combined CBD and THC show promise for promoting dental pulp healing by simultaneously influencing inflammation, nociceptive signaling, tissue repair, angiogenesis, and cell migration. The findings provide new evidence that cannabinoids may have potential applications in future vital pulp therapies designed to preserve and regenerate living dental tissue.
“Introduction: Dental pulp inflammation, caused by caries, trauma, or restorative operations, produces pain and slows regeneration. Cannabidiol (CBD) and Δ9-tetrahydrocannabinol (THC), cannabinoids of Cannabis sativa, have effects on inflammation and pain relief. However, the impact of these factors on dental pulp healing is not understood. This study investigated the combined effects of CBD and THC in controlling inflammation and nociception during dental pulp repair.
Methods: Human dental pulp cells were stimulated with lipopolysaccharide (LPS) and treated with CBD (2.5 μg/mL), THC (0.6 μg/mL), and their combination. Pro-inflammatory cytokines (IL-6, IL-12 and IL-1β) and anti-inflammatory cytokine IL-10 were analysed using qPCR and ELISA, while anti-nociceptive markers (CNR1, CNR2, and TRPV1) were evaluated by qPCR and Western blot. Cell viability, proliferation, and migration assays were performed to evaluate treatment effects on cellular behaviours associated with pulpal repair and regenerative potential.
Results: Compared with either treatment alone, the CBD/THC combination more effectively attenuated pro-inflammatory cytokines IL-6, IL-12, and IL-1β, enhanced CNR1 and CNR2 expression, modulated TRPV1, and increased IL-10 expression. Viability assays determined optimal non-cytotoxic concentrations for treatment. The combination enhanced cell proliferation and migration, promoted mineralized nodule formation, and significantly upregulated markers associated with tissue repair, odontogenic differentiation (DMP1), and angiogenesis (VEGF and bFGF).
Conclusion: Combined CBD and THC show promise for promoting dental pulp healing by modulating inflammation and nociceptive signaling, while supporting odontogenic differentiation, angiogenesis, and cell migration in human dental pulp cells. These findings provide in vitro evidence supporting combined cannabinoid treatment as a therapeutic strategy for vital pulp therapies.”