Evaluating the impact of cannabinoid extracts on chronic pain and quality of life in endometriosis patients – a pilot study

Women with endometriosis and chronic pelvic pain experienced significant improvements after adding a balanced oral THC cannabis extract to their existing treatment. In this prospective pilot study, 27 women completed three months of treatment, with benefits appearing within the first month and continuing through the study period.

Pain intensity fell significantly, along with the number of pain days and the need for conventional pain medicines. Use of both NSAIDs and opioid analgesics decreased, while fatigue, anxiety, central sensitization and pain-related disability also improved.

Quality of life improved across every measured EHP-30 domain, including pain, emotional well-being, work impairment, self-image and sexual relationships. The authors concluded that balanced THC cannabinoid medicines appear to be a potentially effective adjunct treatment for chronic pelvic pain and related symptoms in women with endometriosis.

“Endometriosis is a chronic gynecological disorder characterized by persistent pain and impaired quality of life, with limited effective treatment options. Emerging evidence indicates that cannabinoids may provide analgesic and symptom-relieving effects in chronic pain conditions.

This prospective single-center cohort study investigated the effects of standardized oral cannabis extracts (cannabinoid-based medicinal products, CBMPs) on pain and quality of life in women with endometriosis.

Thirty premenopausal women aged 18-45 years with confirmed endometriosis and chronic pelvic pain were enrolled; 27 completed the 3-month treatment period. Participants received oral CBMPs containing a balanced THC: CBD ratio. Pain intensity, frequency of pain episodes, analgesic use, fatigue, anxiety, central sensitization, disability, and quality of life were assessed using validated questionnaires (VAS, EHP-30, PDI, CFS, GAD-7, CSI).

Significant improvements were observed after one month of treatment, with continued benefit over three months. Pain intensity decreased markedly (p = 0.0004), accompanied by reductions in the number of pain days and analgesic use, including both NSAIDs (e.g., ibuprofen, diclofenac) and opioid analgesics (e.g., tramadol, tilidin, oxycodone) (p < 0.001). Fatigue (p = 0.0013), anxiety (p < 0.0001), central sensitization (p < 0.0001), disability (p < 0.0001), and overall quality of life (EHP-30) improved significantly.

Treatment was well tolerated; side effects were predominantly mild (severity score 1 on a 0-3 scale) and transient, occurring mainly during the titration phase and declining thereafter. Although limited by its single-center design, lack of placebo control, and short follow-up, this study provides preliminary evidence that oral CBMPs may represent a safe and effective adjunct therapy for managing pain and related symptoms in women with endometriosis. Larger randomized controlled trials are warranted to confirm these findings and establish optimal dosing strategies.”

https://pubmed.ncbi.nlm.nih.gov/42771648

“In conclusion, oral CBMPs with balanced THC: CBD ratios seem to be a safe and potentially effective adjunct therapy for chronic pelvic pain and related symptoms in women with endometriosis. By targeting both nociceptive and neuropsychological aspects of the condition, CBMPs can supplement existing pharmacological and lifestyle strategies, providing a more comprehensive approach to symptom management. These findings establish a basis for future controlled studies to refine dosing, investigate mechanisms, and assess long-term outcomes in this complex patient group.”

https://journals.plos.org/plosone/article?id=10.1371/journal.pone.0356768

(+)-Trans-Cannabidiol Is an Agonist at Human CB2 Receptors

A new 2026 study reports that (+)-trans-cannabidiol [(+)-CBD] acts as an agonist at human CB2 cannabinoid receptors, activating a major receptor of the endocannabinoid system involved in immune and inflammatory signaling.

Researchers found that (+)-CBD produced a strong, concentration-dependent CB2 response, reaching roughly 90% of the maximum effect produced by the reference cannabinoid agonist CP55940. Additional testing indicated that the compound acts through the receptor’s primary, or orthosteric, binding site.

The findings show that different molecular forms of cannabidiol can interact with cannabinoid receptors in very different ways. The researchers conclude that (+)-CBD may deserve further study in CB2-sensitive disease states, adding another layer to our understanding of how cannabinoid chemistry can influence the human endocannabinoid system.

“(-)-trans-Cannabidiol ((-)-CBD) is a principal phytocannabinoid from Cannabis sativa. (-)-CBD has complex pharmacology but is a relatively weak inhibitor of CB1 and CB2 receptor signaling. Cannabidiol has two chiral centres and thus four stereoisomers. (+)-trans-CBD ((+)-CBD) has a higher affinity than (-)-CBD at CB1 and CB2, but its pharmacodynamic effects at these receptors are incompletely described.

We examined the activity of (+)-CBD at human CB1 and CB2 receptors using a fluorescence-based assay of membrane potential in AtT20 cells stably expressing CB1 or CB2 receptors.

(+)-CBD produced a rapid, concentration-dependent hyperpolarization in CB2-expressing cells (pEC50 6.63 ± 0.08) with a maximal effect 90% of the response to CP55940. The CB2 response was blocked by pertussis toxin pretreatment and competitively inhibited by the CB2 antagonist AM630 (Schild slope 1.1 ± 0.1). (+)-CBD was a low-efficacy, low-potency CB1 agonist and inhibited somatostatin-receptor effects at high concentrations (10-30 μM). (+)-CBD had no effect on the membrane potential of AtT20 wild-type cells. In silico modeling of ligand interactions with CB2 indicated that (+)-CBD but not (-)-CBD formed an H-bond with Ser285, a residue crucial for agonist activation of CB2.

Our data suggests (+)-CBD acted as a CB2 agonist via the orthosteric binding site on the receptor. Synthetic CBD, including (+)-CBD, has previously been administered in clinical trials, presumably without consideration of its potential CB2 agonist activity.

Given the relative safety of (-)-CBD in people, (+)-CBD may be a useful drug to explore CB2-sensitive disease states.”

https://pubmed.ncbi.nlm.nih.gov/42745361

“This study emphasizes the importance of understanding the molecular actions of the enantiomers of chiral cannabinoids. Although the safety of (+)-CBD cannot simply be assumed to be the same as (−)-CBD, the identification of (+)-CBD as a robust CB2 agonist suggests that (+)-CBD may be worth exploring as a therapeutic agent in chronic inflammatory conditions or other diseases where CB2 activation may prove beneficial.”

https://bpspubs.onlinelibrary.wiley.com/doi/10.1002/prp2.70325

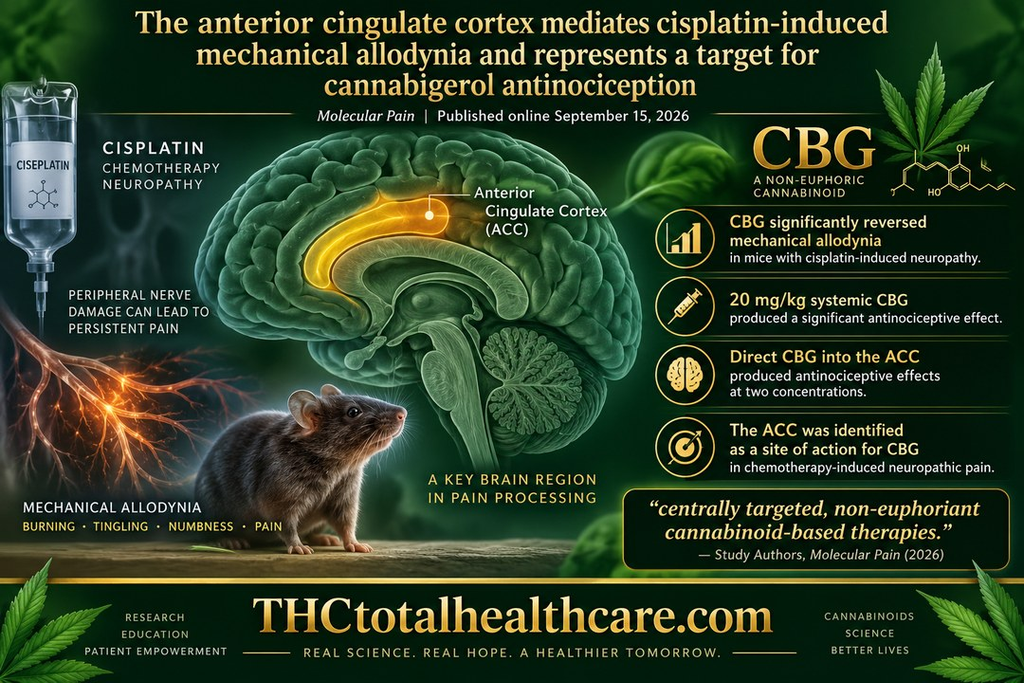
The anterior cingulate cortex mediates cisplatin-induced mechanical allodynia and represents a target for cannabigerol antinociception

Chemotherapy-induced peripheral neuropathy can cause persistent burning, tingling, numbness and pain long after cancer treatment ends. A new 2026 study investigated how the brain contributes to this neuropathic pain and whether cannabigerol (CBG), a non-euphoric cannabinoid, can reduce it.

Using a mouse model of cisplatin-induced neuropathy, researchers found that CBG significantly reversed mechanical allodynia. They also identified the anterior cingulate cortex, a brain region involved in processing pain, as an important part of the neuropathic pain response. Directly administering CBG into this region produced antinociceptive effects.

The findings suggest that CBG can act within central pain-processing circuits and identify the anterior cingulate cortex as a potential target for cannabinoid-based treatment of chemotherapy-induced neuropathic pain. The researchers say the results highlight the potential for “centrally targeted, non-euphoriant cannabinoid-based therapies.”

“Chemotherapy-induced peripheral neuropathy (CIPN) is a prevalent and debilitating consequence of cancer treatment with limited effective therapeutic options. While peripheral nerve injury is a key driver, emerging evidence suggests that maladaptive plasticity within central pain circuits, including the anterior cingulate cortex (ACC), contributes to the maintenance of neuropathic pain.

Here, we tested the hypothesis that the ACC is a critical substrate for cisplatin-induced mechanical allodynia and a target for cannabigerol (CBG)-mediated antinociception.

Adult male C57BL/6 mice received cisplatin (5 mg/kg, i.p., once weekly for four weeks) to induce CIPN. Mechanical allodynia was assessed using electronic von Frey testing.

Systemic administration of CBG (20 mg/kg, i.p.) significantly reversed mechanical allodynia in CIPN mice without affecting baseline thresholds in non-neuropathic animals, indicating a state-dependent effect. Chemogenetic inhibition of ACC neurons using hM4Di DREADDs similarly attenuated mechanical allodynia, identifying the ACC as a functionally relevant component of the CIPN pain state. To determine whether CBG acts within this circuit, bilateral intra-ACC microinjections of CBG (20 nM and 20 µM) were performed, both of which produced transient antinociceptive effects.

These findings demonstrate that the ACC contributes to the maintenance of mechanical allodynia in CIPN and establish this region as a site of action for CBG.

Together, our results support a model in which the ACC represents a convergent cortical mechanism underlying pathological pain and highlight the potential for centrally targeted, non-euphoriant cannabinoid-based therapies.”

https://pubmed.ncbi.nlm.nih.gov/42744343/

“In conclusion, this study identifies the ACC as a hub in the maintenance of mechanical allodynia in a model of CIPN. By demonstrating that chemogenetic inhibition of the ACC reverses hypersensitivity and that both systemic and local administration of CBG produce antinociceptive effects, our findings link circuit-level dysfunction to a pharmacologically targetable mechanism within this region. These results support a model in which increased or dysregulated ACC neuronal activity may represent a convergent feature of pathological pain states. Importantly, these findings demonstrate that CBG can act within the ACC to modulate mechanical allodynia. Future studies identifying the receptor targets and circuit mechanisms through which CBG acts within the ACC will be essential for refining therapeutic strategies for chronic pain.”

https://journals.sagepub.com/doi/10.1177/17448069261491110

Ten-year outcomes of medical cannabis for chronic low back pain: opioid reduction, pain relief, and functional improvement in 1,000 patients

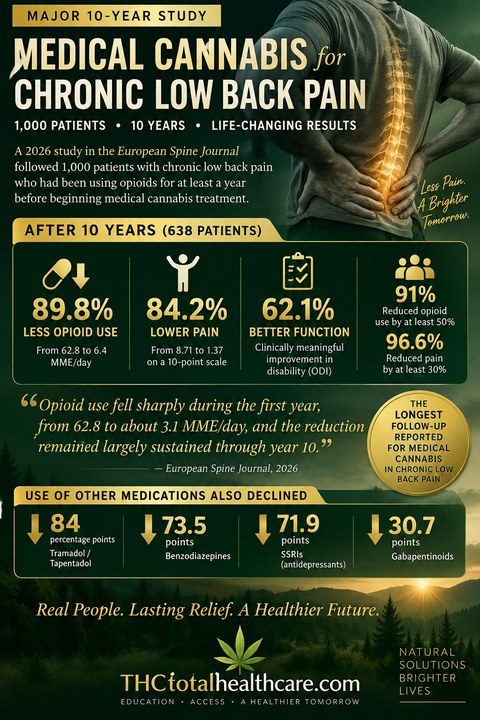
A 2026 study published in the European Spine Journal followed 1,000 patients with chronic low back pain who had been using opioids for at least a year before beginning medical cannabis treatment. Researchers tracked changes in opioid use, pain, disability, and other medications over as long as 10 years.

Among the 638 patients who completed the full 10-year follow-up, average opioid use fell by 89.8%, while pain scores dropped by 84.2%. More than 91% of patients achieved at least a 50% reduction in opioid use, and 96.6% achieved at least a 30% reduction in pain. Disability scores also improved substantially over the study period.

The reductions were not limited to opioids. Use of benzodiazepines, gabapentinoids, antidepressants, and other pain medications also declined. With a decade of follow-up, this study provides unusually long-term evidence that medical cannabis may play an important role in reducing pain, improving function, and decreasing dependence on multiple medications in people living with chronic low back pain.

“Purpose: To evaluate 10-year outcomes of medical cannabis therapy on opioid use, pain intensity, functional disability, concomitant medication use, and adverse events in cannabis-naïve chronic low back pain (CLBP) patients, with particular attention to clinically meaningful outcomes defined by established minimal clinically important difference (MCID) thresholds.

Methods: Single-center longitudinal observational study of 1,000 consecutive cannabis-naïve CLBP patients from a registry database (2015-2024), reported following STROBE guidelines.

Primary outcome: morphine milligram equivalents (MMEQ).

Secondary outcomes: Numeric Rating Scale (NRS) for pain intensity, Oswestry Disability Index (ODI) for functional disability, cannabis dosing patterns, adverse events, and concomitant medication use. Pre-specified MCID thresholds: ≥50% MMEQ reduction, ≥ 30% NRS reduction, ≥ 10-point ODI improvement. Statistical analyses included paired t-tests for completers and linear mixed-effects models for sensitivity analyses.

Results: Of 1,000 enrolled patients, 638 (63.8%) completed 10-year follow-up. Among completers, MMEQ decreased from 62.8 ± 35.7 to 6.4 ± 7.1 mg/day (- 89.8%, p < 0.001); NRS from 8.71 ± 1.23 to 1.37 ± 1.71 (- 84.2%, p < 0.001); ODI from 52.9 ± 11.9% to 36.8 ± 14.9% (16.1-point reduction, – 30.4%, p < 0.001). MCID responders: 91.2% for MMEQ, 96.6% for NRS, 62.1% for ODI. Substantial polypharmacy reductions occurred: tramadol/tapentadol – 84.0% points (pp), benzodiazepines – 73.5 pp, SSRIs – 71.9 pp, gabapentinoids – 30.7 pp. True tolerability adverse events occurred in 11.4% of visits; serious psychiatric events in 0.02%.

Conclusions: In this uncontrolled observational study, medical cannabis therapy was associated with reductions in opioid use, pain intensity, and functional disability over 10 years, accompanied by polypharmacy reduction and acceptable tolerability. Effect sizes substantially exceeded RCT benchmarks (e.g., – 0.6 NRS difference vs. placebo in a recent phase 3 trial), suggesting observational biases contribute to these findings. These hypothesis-generating data warrant validation in randomized controlled trials.”

https://pubmed.ncbi.nlm.nih.gov/42734834

“In this 10-year single-arm observational study, medical cannabis therapy was associated with reductions in opioid use (− 89.8%), pain intensity (− 84.2%), and functional disability (− 30.4%), with high proportions of patients achieving pre-specified MCID thresholds. Substantial polypharmacy reductions and acceptable tolerability were observed.”

https://link.springer.com/article/10.1007/s00586-026-10290-y

Cannabigerol and standardized full-spectrum cannabis extract effects in acute and chronic inflammatory pain models

Cannabigerol (CBG) and a standardized full-spectrum cannabis extract both reduced inflammatory pain and inflammation in a rat study, although their effects developed differently. The full-spectrum extract produced faster pain relief, while repeated CBG treatment eventually restored pain sensitivity to baseline and maintained a longer-lasting antinociceptive effect. Both treatments also prevented increases in the inflammatory marker TNF-α in the spinal cord and blood and helped protect against inflammation-related motor impairment.

“Background: Chronic inflammatory pain is associated with persistent sensory and immune dysregulation. We evaluated the therapeutic efficacy of two cannabinoids formulations-Cannabigerol (CBG) and Standardized Full-Spectrum Cannabis Extract (FULL) in a preclinical model of acute and Chronic inflammatory pain and examined their effects on peripheral and central inflammatory mediators.

Methods: Cannabinoid analgesic effects were assessed in male Wistar Hannover rats using acute (formalin) and chronic inflammatory pain (CFA) models. Treatments were administered at different doses before the formalin test and after CFA as a single dose or once daily for 21 days. Motor function and inflammatory markers (TNF-α and IL-10) were evaluated using actimeter test and ELISA.

Results: In the formalin test, both cannabinoids reduced nociceptive behaviors during Phase I, whereas only FULL produced sustained analgesia during Phase II. In the chronic model, single administration produced no significant effects; while repeated treatment (highest doses) improved mechanical thresholds. FULL (10 mg/kg) produced earlier analgesic effects (day 10), while CBG (10 mg/kg) fully restored baseline sensitivity from day 15 onward. In locomotor assessments, both compounds prevented CFA-induced motor impairments, except at the lowest CBG dose. CFA increased tumor necrosis factor-alpha (TNF-α) in the spinal cord, dorsal root ganglia (DRG), and plasma. Both cannabinoids prevented the CFA-induced increase in TNF-α levels in the spinal cord and plasma. Elevated TNF-α in the DRG persisted despite treatment, indicating region-specific regulation. Interleukin-10 (IL-10) levels were unaffected.

Conclusion: Both cannabinoids exert analgesic and anti-inflammatory effects, with FULL providing faster acute relief and CBG produced a more prolonged antinociceptive effect.”

https://pubmed.ncbi.nlm.nih.gov/42690319

“In conclusion, our study demonstrates that both cannabigerol (CBG) and the Standardized Full-Spectrum Cannabis Extract (FULL) exert significant antinociceptive and anti-inflammatory effects in models of acute and chronic chronic pain of inflammatory origin.”

https://link.springer.com/article/10.1007/s00213-026-07156-y

Effects of delta-9 tetrahydrocannabinol and cannabidiol on cognitive outcomes following acute use of cannabis for chronic pain

In a study of 183 adults using edible cannabis for chronic low back pain, researchers found no significant acute changes in executive function, episodic memory, or processing speed after cannabis use. Participants using CBD-dominant products performed better on working memory than those using CBD + THC one hour after use, while the CBD group also showed more stable verbal-learning scores than participants using THC or mixed CBD/THC products. The findings add useful evidence to the discussion of how different cannabinoid profiles may affect cognition when cannabis is used for chronic pain.

“Rationale: An estimated two-thirds of medical cannabis users in the United States are motivated by chronic pain, but clinical guidance remains guarded as to whether the potential benefit of cannabinoids for pain outweighs potential risks, such as effects on cognition.

Objectives: In a study where participants experienced benefits of cannabinoids for pain and tension, we evaluated cannabis effects on executive function, processing speed, memory, and verbal learning following acute use for chronic, non-specific low back pain.

Methods: Participants were in one of three self-selected edible cannabis groups: a) CBD-dominant, b) THC-dominant, or c) a mixed ratio of CBD to THC and completed a battery of cognitive tasks at pre-use, 1 h post-use use, and 2 h post-use.

Results: Among 183 participants (56.8% female; Mage = 45.6), those in the group using CBD outperformed participants using CBD + THC 1 h post use in working memory and produced more stable scores in verbal learning after use than participants using THC or CBD + THC. Additionally, while older age was associated with better working memory in the CBD group before use, that relationship was progressively attenuated over the subsequent timepoints. There were no significant effects of cannabis use on cognition in the domains of executive function, episodic memory, or processing speed.

Conclusions: Given the ubiquity of cannabis use for chronic pain and the ongoing call for more data, this study is relevant for informing clinical guidance on whether, and how, cannabis could be used in this context. In particular, understanding the acute impact on cognition from cannabis is critical, as cognitive functioning directly affects patients’ daily lives and quality of life.”

https://pubmed.ncbi.nlm.nih.gov/42678518

“In summary, these findings support CBD’s potential to preserve cognitive performance in the context of chronic pain, contrasting with the more variable effects of THC across cognitive domains. The observed influence of age, particularly among those using CBD, suggests that both cannabinoid composition and individual factors shape cognitive outcomes following acute cannabinoid use.”

https://link.springer.com/article/10.1007/s00213-026-07157-x

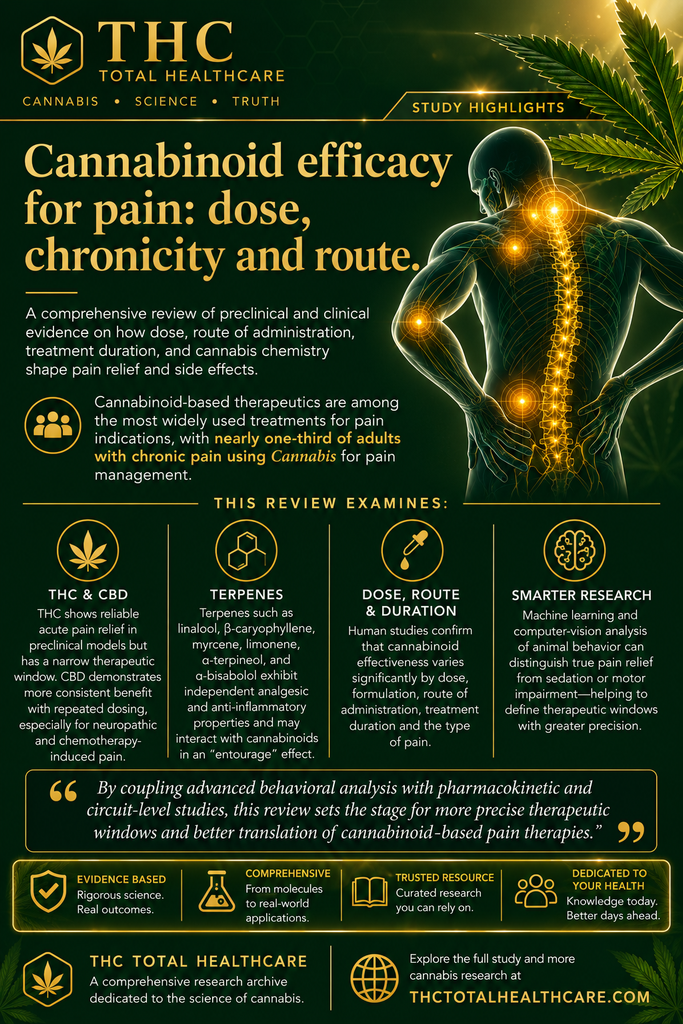
Cannabinoid efficacy for pain: dose, chronicity and route

Cannabinoid pain relief depends on more than whether THC or CBD is used. Dose, route of administration, treatment duration and the type of pain can all influence whether a cannabis-based therapy provides meaningful analgesia or produces unwanted effects. This review examines those variables across preclinical and clinical research, while also considering the independent and combined roles of cannabis-derived terpenes.

“Cannabis-based therapies are widely used for chronic pain, yet their mechanisms and therapeutic windows remain incompletely defined. This review synthesizes preclinical and clinical evidence on how dose, route of administration, treatment duration, and chemical composition shape analgesic efficacy and adverse-effect liability for Δ9-tetrahydrocannabinol (THC), cannabidiol (CBD), and select cannabis-derived terpenes.

Across rodent pain models, acute THC reliably produces antinociception, but its therapeutic window is narrow because analgesic doses overlap with CB1 receptor-mediated side effects such as sedation, hypothermia, hyperphagia, and motor impairment. Repeated THC exposure leads to tolerance and dependence.

In contrast, CBD shows limited acute efficacy in naïve and inflammatory models but demonstrates more consistent benefit with repeated dosing in neuropathic and chemotherapy-induced pain, often without cannabimimetic adverse effects.

Terpenes such as linalool, β-caryophyllene, myrcene, limonene, α-terpineol, and α-bisabolol exhibit independent antinociceptive and anti-inflammatory properties and are thought to pharmacologically interact with cannabinoids in a dose-, ratio-, and route-dependent “entourage” effect that either enhance or constrain therapeutic benefit.

This review also focuses on integrating machine learning-based behavioral phenotyping of rodents to refine cannabinoid analgesia preclinical research. Computer vision pose-estimation and unsupervised clustering approaches enable high-resolution quantification of spontaneous and evoked natural behaviors, allowing the analytical dissociation of true analgesia from sedation, ataxia, or reduced exploration. By coupling these behavioral pipelines with pharmacokinetic and circuit-level analyses, emerging frameworks will define therapeutic windows with greater precision and improve the translational relevance of cannabinoid-based pain therapeutics.”

https://pubmed.ncbi.nlm.nih.gov/42661783

“Cannabinoid-based therapeutics are among the most widely used treatments for pain indications, with nearly one-third of adults with chronic pain using Cannabis for pain management.”

“Taken together, the studies reviewed here demonstrate that the analgesic efficacy of THC, CBD, and Cannabis-derived terepenes is dependent on dose, route of administration, treatment chronicity, and chemical composition.”

https://www.frontiersin.org/journals/neuroscience/articles/10.3389/fnins.2026.1888863/full

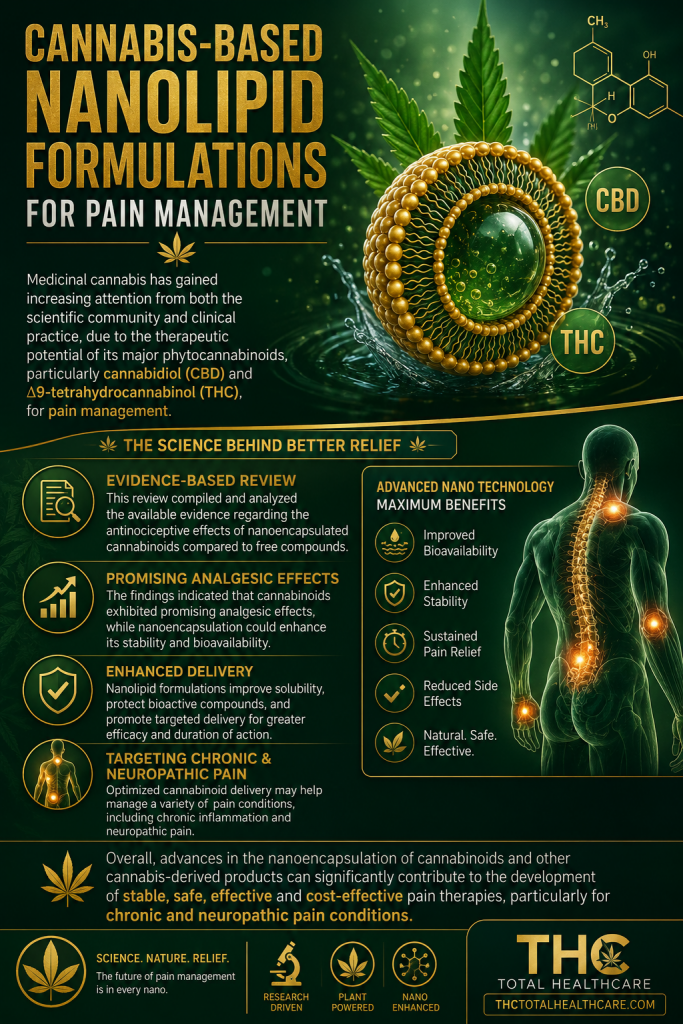
Cannabis-Based Nanolipid Formulations for Pain Management

Cannabinoids such as CBD and THC show promising analgesic effects, but poor stability and bioavailability can limit their therapeutic performance. This review found that nanoencapsulation may improve cannabinoid stability, delivery, and pain-relieving potential across acute, chronic, and neuropathic pain models. The authors concluded that cannabinoid nanoformulations could help support the development of more stable, safe, effective, and accessible therapies, particularly for chronic and neuropathic pain.

“Medicinal cannabis has gained increasing attention from both the scientific community and clinical practice, due to the therapeutic potential of its major phytocannabinoids, particularly cannabidiol (CBD) and Δ9-tetrahydrocannabinol (THC), for pain management.

This review compiled and analyzed the available evidence regarding the antinociceptive effects of nanoencapsulated cannabinoids compared to free compounds. The published works have explored some pharmaceutical formulations and administration routes on different acute, chronic and neuropathic pain experimental models.

The findings indicated that cannabinoids exhibited promising analgesic effects, while nanoencapsulation could enhance its stability and bioavailability.

Despite these advances, the number of reports investigating nanostructured cannabinoid-based systems remains limited, with a predominance of preclinical research. A recurrent lack of structural information and quality control data for such works was also noted. Furthermore, there were not identified any research regarding the nanoencapsulation of full-spectrum cannabis oils or whole cannabis extracts, highlighting a significant gap in the current literature.

Overall, nanoencapsulation emerges as a versatile strategy to overcome the intrinsic limitations of cannabinoids and expand its clinical applicability for pain treatment. Nevertheless, further efforts are required to determine standardized methodologies, facilitating the translation of preclinical findings into clinical practice, in order to provide stable, safe, effective and more accessible cannabinoid-based therapies.”

https://pubmed.ncbi.nlm.nih.gov/42514922

“Overall, advances in the nanoencapsulation of cannabinoids and other cannabis-derived products can significantly contribute to the development of stable, safe, effective and cost-effective pain therapies, particularly for chronic and neuropathic pain conditions.”

https://www.mdpi.com/1999-4923/18/7/844


Lower Pain Intensity Is Associated with the Use of Recreational Edible Cannabis Products Containing Delta-9-Tetrahydrocannabinol: A Secondary Analysis in Adults Self-Managing Their Chronic Low Back Pain

Adults using edible cannabis products to self-manage chronic low-back pain reported lower pain intensity on days they used products containing THC. Over 14 days, pain also declined among participants using products with relatively equal amounts of THC and CBD, with 36.6% achieving at least a 30% reduction in pain intensity. The researchers concluded that lower daily pain was associated specifically with THC-containing products, while higher CBD doses may attenuate some of THC’s pain-relieving association.

“Background/Objectives: Current literature regarding the efficacy of cannabis to reduce chronic pain intensity is mixed. Despite growing accessibility throughout the U.S., it is still unclear if the naturalistic use of recreational cannabis edible products is associated with decreases in pain intensity on days of use or longitudinally, and if these associations are dependent on the doses of delta-9-tetrahydrocannabinol (THC) and cannabidiol (CBD) being consumed. 

Methods: The trial (NCT03522324) from which these data were pulled was pre-registered in April 2018. Participants (N = 243; 56% female; mean age = 46 ± 12 years) with self-reported chronic low-back pain selected a recreational edible cannabis product to use exclusively, ad libitum, for 14 days. Labeled THC and CBD potency were used to determine product group: CBD-dominant (n = 97), THC + CBD (n = 112), or THC-dominant (n = 34). Participants completed daily surveys indicating current pain intensity (PROMIS; 0-10 scale), use or non-use of their product, and cannabinoid dose (THC and CBD). 

Results: Linear mixed effects showed a significant use × group interaction (p = 0.002), indicating that pain intensity was significantly lower on days of use in THC-dominant (b = -0.66, 95% CI [-0.94,-0.37]) and THC + CBD (b = -0.41, 95% CI [-0.57,-0.25]) groups compared to days when cannabis was not used. A significant group × time interaction (p = 0.02) indicated that pain intensity significantly decreased from day 1 to day 14 in those using THC + CBD products (b = -0.05, 95% CI [-0.07,-0.03]), with 36.6% of participants in the THC + CBD group experiencing ≥30% reduction in pain intensity from day 1 to day 14. Increasing doses of THC (b = -0.02, 95% CI [-0.04, -0.01]), not CBD (b = 0.003, 95% CI [-0.03, 0.01]), were associated with significantly lower pain intensity on days following product use, with increasing doses of CBD diminishing the impact of THC dose (b = 0.02, 95% CI [0.01, 0.04]). 

Conclusions: These findings indicate a complex relationship between THC, CBD, and pain intensity associated with the naturalistic use of recreational cannabis edible products. Lower daily pain intensity was associated with the use of products containing THC; however, dose models indicate that this association may be attenuated at higher doses of CBD. Additionally, only products containing relatively equal amounts of THC and CBD were associated with lower pain intensity after 14 days of observation.”

https://pubmed.ncbi.nlm.nih.gov/42512114

“Daily data collected over 14 days of naturalistic cannabis use demonstrated that reductions in participants’ current pain intensity were associated with the use of cannabis edible products, but only in products that contained THC. More frequent use of these products in the previous 24 h was associated with improved reductions in pain intensity.”

https://www.mdpi.com/2227-9059/14/7/1642


Cannabidiol in the anterior insular cortex attenuates chronic neuropathic pain and comorbid anxiety- and depression-like behaviors: involvement of CB1 and 5-HT1A receptor signaling

Chronic neuropathic pain often occurs alongside anxiety and depression, making treatment more difficult than addressing pain alone. In this preclinical study, researchers examined CBD activity within the anterior insular cortex, a brain region involved in pain perception and emotional processing. CBD reduced neuropathic pain while also improving anxiety- and depression-like behaviors, with the effects linked to CB1 and 5-HT1A receptor signaling. The findings suggest that CBD may influence overlapping neural pathways involved in both chronic pain and its emotional consequences, supporting further investigation of cannabinoid-based approaches for complex pain conditions.

“Background: Chronic neuropathic pain (NP) is frequently accompanied by anxiety- and depression‑like symptoms, reflecting maladaptive interactions between nociceptive and affective brain networks. The anterior insular cortex (AIC) integrates sensory and emotional dimensions of pain and represents a potential target for pharmacological modulation. Cannabidiol (CBD) exhibits analgesic and anxiolytic/antidepressant‑like properties through interactions with endocannabinoid and serotonergic systems.

Objectives: We investigated whether CBD microinjection into the AIC modulates NP and its affective comorbidities, and whether these effects depend on CB1 and 5‑HT1A receptors.

Methods: Male Wistar rats were subjected to chronic constriction injury (CCI) of the sciatic nerve. Fourteen days later, guide cannulae were implanted into the AIC. On day 21 post‑CCI, animals received intra‑AIC microinjections of CBD (15, 30, or 60 nmol/200 nL) or vehicle. Mechanical (von Frey test) and cold (acetone test) allodynia, anxiety‑like behavior (open field and elevated plus maze tests), and depression‑like behavior (forced swim and sucrose spray tests) were assessed by different psychobiological tests. The role of cannabinoid and serotonergic receptors was addressed by intra‑AIC pretreatment with either the CB1 receptor antagonist AM251 or the 5‑HT1A receptor antagonist WAY-100,635 in independent groups.

Results: AIC pretreatment with CBD dose‑dependently reduced mechanical and cold allodynia and anxiety‑ and depression‑like behaviors, with the most robust effects observed at 60 nmol. AIC Pretreatment with either AM251 or WAY-100,635 abolished the antinociceptive and affective effects of CBD.

Conclusion: CBD administration within the AIC produces integrated analgesic, anxiolytic, and antidepressant-like effects in a model of neuropathic pain. These effects are consistent with the involvement of CB1 and 5-HT1A receptor signaling. The findings identify the AIC as a relevant cortical substrate linking nociceptive and affective processes and support CBD as a promising psychopharmacological strategy for NP associated with emotional comorbidities.”

https://pubmed.ncbi.nlm.nih.gov/42390818

“In conclusion, this study demonstrates that CBD microinjection into the AIC attenuates mechanical and cold allodynia while also reducing anxiety- and depression-like behaviors in an experimental model of NP.”

“Overall, these findings highlight the AIC as a potential neural substrate involved in the interaction between chronic pain and its emotional comorbidities and identify CBD as a promising psychopharmacological approach for NP conditions associated with affective dysfunction.”

https://link.springer.com/article/10.1007/s00213-026-07116-6